Where Bright Smiles Begin.

Lower Teeth Calculus and Floor-of-Mouth Lesion: Comprehensive Dental Case Analysis and 14-Day Treatment Guide
Image:
Severity:
Teeth Problems:
Clinical Assessment: Heavy Calculus on the Lower Front Teeth and a Lesion Under the Tongue
Understanding the Clinical Significance
Heavy dental calculus around the lower front teeth, particularly behind the lower incisors, is a common finding in general dental practice. This region is especially prone to calculus accumulation because the openings of the submandibular and sublingual salivary ducts are located nearby. Minerals in saliva can gradually harden dental plaque, forming deposits that cannot be completely removed by ordinary brushing.
However, when a patient also presents with a lump, ulcer, swelling, or unusual tissue change on the floor of the mouth, the findings should not automatically be attributed to calculus.
The key clinical principle is to assess the dental deposits and the soft-tissue lesion as two potentially related but distinct problems. A dentist must examine the teeth, periodontal tissues, salivary ducts, and floor-of-mouth tissues to determine whether the findings are connected.
1. Why Calculus Accumulates Behind the Lower Front Teeth
Dental calculus, also known as tartar, forms when plaque mineralizes on tooth surfaces. The lingual surfaces of the lower anterior teeth are particularly susceptible because of their proximity to major salivary duct openings.
Common contributing factors include:
-
Inadequate removal of plaque along the gumline.
-
Irregular professional dental cleaning.
-
Crowded or overlapping lower front teeth.
-
Existing gum inflammation and periodontal pockets.
-
Individual differences in saliva composition and flow.
Once plaque has hardened into calculus, brushing and flossing cannot reliably remove it. Professional scaling is required to remove these deposits safely.
2. What Problems Can Lower Teeth Calculus Cause?
Calculus creates a rough surface that encourages additional plaque accumulation. The bacterial biofilm associated with these deposits can contribute to gingivitis and periodontal disease.
Possible clinical findings include:
-
Red, swollen, or bleeding gums.
-
Persistent bad breath.
-
Gum tenderness.
-
Gingival recession.
-
Periodontal pocket formation.
-
Progressive loss of supporting bone in advanced periodontitis.
It is important to distinguish the calculus itself from the inflammatory process surrounding it. Calculus is a contributing plaque-retentive factor, while the bacteria in plaque and the body's inflammatory response play central roles in periodontal disease.
Important: Heavy calculus does not, by itself, establish that a patient has advanced periodontitis. A periodontal examination is needed to assess pocket depths, attachment loss, mobility, and any need for dental radiographs.
3. What Does a Lesion on the Floor of the Mouth Mean?
The floor of the mouth is the soft-tissue area beneath the tongue. A lesion in this region may appear as a bump, swelling, ulcer, red or white patch, or a firm area of tissue.
Possible causes include:
Salivary duct obstruction or a salivary stone: A stone affecting a salivary duct may cause swelling beneath the tongue or under the jaw, sometimes becoming more noticeable during meals.
Mucous retention or extravasation lesion: A ranula is a mucus-filled swelling associated with the sublingual salivary gland. It may appear as a soft, sometimes bluish swelling on the floor of the mouth.
Traumatic ulcer or irritation: Sharp tooth edges, accidental biting, or local irritation may cause a painful ulcer or inflamed tissue.
Developmental or normal anatomical variation: Some structures beneath the tongue, including the sublingual folds and salivary duct openings, may be mistaken for abnormal growths.
Infection or inflammatory disease: Localized infection, salivary gland inflammation, or other oral inflammatory conditions may cause swelling or tenderness.
Potentially serious oral disease: Persistent ulcers, unexplained lumps, firm lesions, red or white patches, or lesions that bleed without an obvious cause require professional assessment to exclude oral potentially malignant disorders and oral cancer.
The appearance of a lesion alone is not sufficient to establish its diagnosis. Depending on the findings, a dentist may recommend specialist referral, imaging, or biopsy.
4. Are Lower Teeth Calculus and a Floor-of-Mouth Lesion Connected?
They can coexist, but one does not necessarily cause the other.
Heavy calculus may contribute to local gum inflammation, bleeding, and plaque retention. A lesion beneath the tongue may instead arise from a salivary duct problem, trauma, a benign soft-tissue condition, infection, or another cause.
A dentist should determine whether the lesion is located in the gingiva beside the teeth, at a salivary duct opening, within the sublingual tissues, or elsewhere in the oral cavity.
This anatomical distinction is essential because treatment for periodontal calculus is different from treatment for a salivary gland lesion or a suspicious soft-tissue growth.
5. Recommended Dental Examination
A structured assessment may include the following steps:
Step 1 — Medical and dental history
The clinician asks when the lesion first appeared, whether it is painful, whether it changes in size, and whether swelling occurs during meals. Smoking, alcohol exposure, medications, previous dental treatment, and relevant medical conditions may also influence the assessment.
Step 2 — Examination of the lower teeth and gums
The dentist evaluates the amount and location of calculus, gum inflammation, bleeding, periodontal pocket depths, recession, tooth mobility, and any signs of dental infection.
Step 3 — Examination of the floor of the mouth
The clinician inspects the lesion's location, color, surface, size, consistency, and tenderness. The tongue, salivary duct openings, and surrounding tissues are also examined.
Step 4 — Additional investigations when indicated
Dental radiographs may help assess periodontal bone loss or suspected tooth-related infection. Ultrasound or other imaging may be appropriate when a salivary stone or deeper swelling is suspected. A persistent or suspicious soft-tissue lesion may require referral and biopsy.
Step 5 — A diagnosis-directed treatment plan
Treatment should follow the clinical findings rather than assuming that calculus is responsible for every abnormality in the region.
6. Professional Treatment for Lower Teeth Calculus
The usual treatment for accessible supragingival calculus is professional scaling using appropriate dental instruments or ultrasonic equipment.
If periodontal examination identifies deeper deposits and periodontal disease, subgingival instrumentation or scaling and root planing may be indicated. Treatment is tailored to the patient's periodontal condition.
Patients should not attempt to scrape calculus off with needles, blades, metal tools, or household instruments. These practices can damage the gums, injure the floor of the mouth, introduce infection, and delay appropriate diagnosis.
After professional cleaning, patients should maintain daily plaque control through twice-daily brushing with fluoride toothpaste, gentle cleaning along the gumline, and interdental cleaning appropriate to their anatomy.
7. A Safe 14-Day Dental Management Framework
A 14-day plan can organize assessment, treatment, and follow-up, but it is not a universal healing schedule. A lesion that needs investigation should not be left untreated simply to complete a two-week observation period.
Days 1–2: Examination and diagnosis
Arrange a dental assessment for the calculus and floor-of-mouth lesion. The clinician should determine whether there is periodontal disease, a salivary duct problem, trauma, infection, or another soft-tissue condition.
Days 2–4: Initial treatment
If appropriate, undergo professional scaling and receive individualized oral hygiene instructions. If the lesion suggests a salivary gland problem, infection, or another condition, follow the specific treatment or referral plan instead of assuming scaling will resolve it.
Days 4–7: Monitor symptoms
Follow the dentist's instructions. Monitor gum bleeding, tenderness, swelling, bad breath, and any change in the lesion. Avoid repeatedly touching, squeezing, or scraping the area.
Days 7–14: Reassessment when indicated
Return for review if recommended by the dentist. A lesion that persists, enlarges, becomes firmer, or develops unexplained bleeding requires reassessment. Suspicious lesions should be referred promptly rather than observed for 14 days without evaluation.
At any time: Seek urgent care for warning signs
Rapidly increasing swelling beneath the tongue or jaw, difficulty swallowing, difficulty breathing, drooling, or swelling that elevates or pushes the tongue upward can indicate a serious infection or airway threat. Seek emergency medical care immediately.
8. Clinical Takeaway
Heavy calculus behind the lower front teeth is common and is treatable through professional dental cleaning and consistent plaque control. A simultaneous lesion on the floor of the mouth, however, requires a separate, careful assessment.
The safest approach is to remove calculus when indicated, evaluate periodontal health, identify the lesion's anatomical origin, and select additional investigations or treatment based on the findings. No single visual description or 14-day schedule can reliably diagnose every lesion in this area.
Full Dental Case Analysis
1. Overall Photographic Assessment
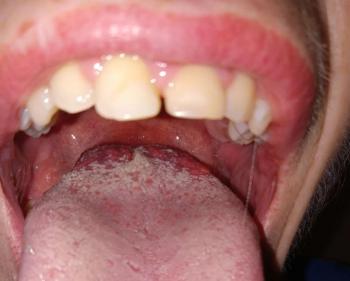
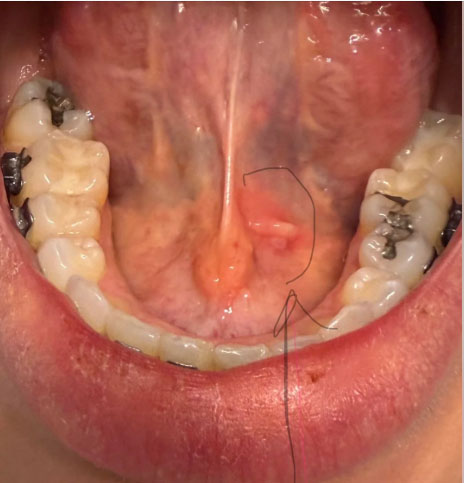
The photograph provides a good view of the lower teeth, tongue, floor of the mouth, and surrounding oral tissues.
The most noticeable dental finding is a visible accumulation of yellowish to brownish material along the tongue-facing surfaces of the lower anterior teeth. This appearance is compatible with dental calculus, commonly called tartar.
There also appears to be localized gingival irritation around the lower teeth.
The circled area on the floor of the mouth is a separate finding and should not automatically be attributed to the dental calculus.
The photograph alone cannot determine whether the patient has simple gingivitis, periodontitis, a salivary-duct abnormality, trauma, or another oral condition.
2. Lower Teeth and Calculus Assessment
The lower anterior teeth appear to have a noticeable calculus burden, particularly along the lingual surfaces.
This type of hardened deposit cannot reliably be removed through normal brushing.
Professional scaling is appropriate when calculus is confirmed clinically.
The dentist should also determine whether additional calculus is present below the gumline because subgingival deposits cannot be adequately assessed from this photograph.
3. Is Full-Mouth Scaling Necessary?
Full-mouth scaling may be appropriate, but the decision should follow a periodontal examination.
The dentist should evaluate every tooth for:
- Plaque accumulation.
- Calculus above the gumline.
- Calculus below the gumline.
- Bleeding during periodontal probing.
- Pocket depth.
- Gum recession.
- Clinical attachment loss.
- Tooth mobility.
- Furcation involvement.
- Radiographic bone loss.
If the patient has generalized gingival inflammation without attachment or bone loss, professional scaling may be appropriate.
If periodontal pockets, attachment loss, and bone loss are identified, treatment may need to progress from ordinary cleaning to periodontal therapy.
The American Dental Association explains that scaling and root planing is a deep cleaning procedure used below the gumline when periodontal pockets are sufficiently deep.
4. Possible Gingivitis
The visible gum tissue appears somewhat inflamed.
Possible gingivitis should therefore be considered.
However, gingivitis and periodontitis are not interchangeable diagnoses.
Gingivitis involves inflammation without the attachment and bone destruction that defines periodontitis.
A periodontal probe is needed to determine whether deeper periodontal disease exists.
5. Possible Periodontitis
Periodontitis cannot be confirmed from this photograph.
The presence of calculus increases the reason to investigate, but calculus alone does not prove that periodontal bone loss has occurred.
The dentist should obtain periodontal measurements and appropriate radiographs if indicated.
The American Dental Association classifies periodontitis according to factors including attachment loss, bone loss, severity, complexity, extent, and evidence of disease progression.
6. Examination of the Circled Area
The circled region beneath the tongue deserves a separate clinical examination.
It appears to contain a localized raised or prominent soft-tissue structure.
One possibility is that this represents normal anatomy associated with the sublingual or salivary-duct region. However, the photograph is not sufficient to establish that.
Other possibilities include localized irritation, inflammation, trauma, salivary-duct obstruction, cystic change, or another mucosal lesion.
The dentist should determine:
- How long it has been present.
- Whether it is painful.
- Whether it has increased in size.
- Whether it is soft, firm, or fluctuant.
- Whether it changes during eating.
- Whether saliva flows normally from the nearby duct.
- Whether there is ulceration.
- Whether there is bleeding.
- Whether there is a white or red surface change.
- Whether there are enlarged lymph nodes.
The important point is that the circled area should not simply be assumed to be caused by tartar.
7. Recommended Diagnostic Process
First Appointment
The first appointment should establish the diagnosis before extensive treatment.
Recommended examination:
- Complete dental examination.
- Full periodontal charting.
- Pocket-depth measurements.
- Bleeding-on-probing assessment.
- Tooth mobility evaluation.
- Recession measurement.
- Calculus assessment.
- Examination of the tongue.
- Examination of the entire floor of the mouth.
- Assessment of the circled area.
- Radiographs when clinically indicated.
Radiographs are particularly important when the dentist needs to determine whether supporting bone has been lost.
8. Scaling Treatment
If the examination confirms mainly supragingival calculus and gingival inflammation, professional scaling can remove the deposits and allow the gums to recover.
If subgingival calculus and periodontal pockets are identified, scaling and root planing may be required.
The ADA describes scaling as removal of plaque and tartar above and below the gumline and root planing as treatment of affected root surfaces. Multiple visits may be necessary depending on the extent of disease.
9. Suggested Treatment Sequence
Visit 1
Comprehensive examination.
Periodontal charting.
Assessment of the floor-of-mouth finding.
Radiographs if indicated.
Initial professional debridement or scaling if appropriate.
Oral-hygiene instruction.
Visit 2
Complete remaining scaling.
Perform deeper periodontal instrumentation where clinically indicated.
Address localized areas that cannot be adequately cleaned during the first visit.
Follow-Up
Reassess gum inflammation and periodontal measurements.
Determine whether periodontal pockets remain.
Determine whether additional periodontal treatment is necessary.
For established periodontitis, the ADA notes that periodontal tissues may require approximately four weeks to demonstrate the optimal effects of nonsurgical therapy.
10. What Happens During the First 14 Days?
Days 1 to 3
The teeth and gums may feel sensitive following significant calculus removal.
Minor bleeding or gum tenderness may occur.
This can be particularly noticeable when previously inflamed tissues are professionally cleaned.
Days 4 to 7
Gingival inflammation should begin decreasing if plaque control is effective.
The gums may appear less swollen.
Bleeding should gradually decrease.
Days 7 to 14
The patient may notice a significant improvement in gum comfort and appearance.
However, this does not mean periodontal disease has necessarily been completely treated.
Deep pockets and bone loss cannot be judged simply by looking at the gums.
Around 4 Weeks
A more meaningful periodontal reassessment may be appropriate.
The dentist can compare periodontal measurements with the initial examination.
The ADA notes that periodontal tissues can require approximately four weeks to demonstrate the optimal effects of nonsurgical periodontal therapy.
11. What Could Scale Up If Treatment Is Delayed?
If the patient has only gingivitis, the condition may remain reversible with appropriate professional cleaning and effective plaque control.
If the patient already has periodontitis, delaying treatment can allow inflammation and bacterial accumulation to persist.
The potential progression is:
Plaque accumulation
Calculus formation
Persistent gingival inflammation
Periodontal pocket development
Attachment loss
Supporting bone loss
Tooth mobility
Possible tooth loss
This progression is not inevitable in every patient. The actual risk can only be determined after periodontal examination and appropriate diagnostic testing.
12. Why 14 Days Should Not Be Considered the Final Deadline
A 14-day period is useful for observing early improvement, but it should not be considered the complete healing period for periodontal disease.
The patient may look considerably better after two weeks while deeper periodontal problems remain.
For that reason, the treatment endpoint should be based on clinical measurements rather than appearance alone.
13. Home Care During the 14-Day Period
Brush twice daily with fluoride toothpaste.
Clean between the teeth every day.
Use a soft toothbrush unless the dentist recommends otherwise.
Clean the tongue gently.
Avoid attempting to scrape calculus from the teeth with metal instruments at home.
Follow any specific mouthwash or medication instructions provided by the dentist.
Avoid smoking or tobacco because it can negatively affect periodontal health and healing.
14. When the Floor-of-Mouth Finding Requires Faster Evaluation
The patient should seek earlier professional assessment if the circled area:
Becomes larger.
Becomes significantly painful.
Develops pus.
Bleeds spontaneously.
Becomes ulcerated.
Becomes hard or fixed.
Causes difficulty swallowing.
Causes difficulty moving the tongue.
Is accompanied by neck swelling.
Is associated with fever.
Produces rapidly increasing swelling.
A persistent unexplained oral lesion should not simply be ignored.
15. Recommended Case Severity
Based strictly on the photograph:
Visible calculus: Moderate to significant
Gingival inflammation: Possible
Gingivitis: Possible
Periodontitis: Cannot be confirmed photographically
Bone loss: Cannot be determined from this photograph
Subgingival calculus: Requires clinical examination
Floor-of-mouth finding: Requires direct examination
Full-mouth scaling: Potentially appropriate after examination
Scaling and root planing: Only if periodontal findings justify it
Four-week periodontal reassessment: Appropriate when periodontitis is confirmed
16. Finding a Nearby Dental Clinic
The patient's exact location is not provided, so a specific clinic cannot reliably be called the nearest clinic.
Your Cebu Dental Implants directory provides a location-based search designed to help patients find dental clinics near their area. The page includes location filters and a "Find dental clinic nearest to your place" search function.
Use the directory here:
Find a Dental Clinic Near You – Cebu Dental Implants Directory
The directory currently includes clinics across Cebu City, Mactan, Talisay, and other areas, with services/categories including bleeding gums, bone loss, gingivitis, gum disease, oral infection, plaque, and related dental conditions.
17. Recommended Patient Action
The most appropriate next step is:
Dental examination
Periodontal charting
Professional scaling
Radiographs if clinically indicated
Evaluation of the floor-of-mouth finding
Follow-up periodontal assessment
Do not wait 14 days before obtaining the initial examination.
The 14-day period should be considered an observation period after appropriate professional treatment, not a period in which potentially significant disease is left untreated.
Lower Teeth Calculus and Floor-of-Mouth Lesion: Expert Dental Analysis
Expert Analysis: Lower Teeth Calculus and a Floor-of-Mouth Lesion
When heavy calculus is present around the lower front teeth, particularly near the tongue-side surfaces, it can contribute to persistent gum inflammation, bleeding, bad breath, gum recession, and difficulty maintaining effective oral hygiene.
However, calculus and a lesion in the floor of the mouth should not automatically be assumed to have the same cause. A dental professional needs to examine the mouth directly to determine whether the floor-of-mouth finding is related to local irritation, infection, a salivary-gland problem, trauma, or another condition.
What a Dental Expert Would Look For
A dentist or oral-health professional would typically assess:
-
The amount and location of hardened calculus.
-
Gum redness, swelling, bleeding, recession, and periodontal pocket depth.
-
Tooth mobility or changes around the supporting bone.
-
Plaque accumulation underneath and around the calculus.
-
The appearance, size, color, texture, and location of the floor-of-mouth lesion.
-
Whether the lesion is painful, ulcerated, bleeding, firm, soft, or associated with swelling.
-
Whether there is swelling beneath the tongue or around a salivary-gland duct.
-
The presence of enlarged lymph nodes or other concerning oral findings.
-
Whether dental X-rays or other imaging are needed.
Why Lower Front Teeth Commonly Develop Calculus
The tongue-side surfaces of the lower front teeth are particularly prone to calculus accumulation because they are close to the openings of major salivary glands. Minerals in saliva can harden dental plaque into calculus.
Once calculus has formed, ordinary brushing cannot reliably remove it. Professional scaling is generally required.
Trying to scrape calculus away with sharp household objects can injure the gums, damage tooth surfaces, or introduce infection.
Calculus vs. a Floor-of-Mouth Lesion
These are two different clinical findings.
Calculus is hardened mineralized dental plaque attached to tooth surfaces.
A floor-of-mouth lesion is any abnormal area involving the tissue beneath the tongue. It may have many possible causes, including irritation, trauma, infection, salivary-gland disorders, benign growths, or potentially more serious disease.
Therefore, the presence of heavy calculus does not prove that a nearby floor-of-mouth lesion is caused by calculus.
Expert Voice: What Should Happen Next?
Dental expert perspective: The priority is to treat the obvious periodontal problem while simultaneously evaluating any persistent or unusual lesion in the floor of the mouth. Cleaning the teeth is important, but it should not be used as a substitute for examination of a suspicious soft-tissue finding.
A dentist may recommend professional scaling and improved home care for calculus and gingival inflammation. If the floor-of-mouth lesion does not resolve, has concerning characteristics, or cannot be confidently identified, referral to an oral medicine specialist, oral and maxillofacial surgeon, or other appropriate specialist may be necessary.
Accurate Medical Guidance: When Should You Seek Urgent Care?
Seek prompt dental or medical evaluation if a floor-of-mouth lesion:
-
Persists or does not heal within about 2 weeks.
-
Continues to enlarge.
-
Becomes increasingly painful or swollen.
-
Bleeds without an obvious cause.
-
Becomes unusually firm or develops an irregular appearance.
-
Causes persistent numbness.
-
Is associated with a neck lump or enlarged lymph node.
-
Causes difficulty swallowing.
-
Causes difficulty moving the tongue.
-
Causes unexplained weight loss or persistent oral symptoms.
Emergency Warning Signs
A rapidly increasing swelling beneath the tongue or jaw can occasionally affect the airway.
Seek emergency medical care immediately if oral or floor-of-mouth swelling is accompanied by:
-
Difficulty breathing.
-
Severe difficulty swallowing.
-
Drooling because swallowing is difficult.
-
Rapidly increasing swelling.
-
Significant tongue elevation or displacement.
-
A muffled or markedly changed voice.
These symptoms should not be managed by waiting for a routine dental appointment.
14-Day Follow-Up: What Should Be Evaluated?
A 14-day follow-up can be useful when monitoring a mouth lesion or significant gum inflammation, but the exact follow-up interval depends on the clinical findings.
At follow-up, the clinician should reassess:
-
Has the lesion become smaller?
-
Has its color or surface changed?
-
Is pain or tenderness improving?
-
Has swelling decreased?
-
Are the gums bleeding less after professional cleaning and improved oral hygiene?
-
Is there persistent calculus that requires additional periodontal treatment?
-
Does the lesion still require specialist assessment or further investigation?
Improvement is reassuring, but persistence does not necessarily identify the cause. A lesion that remains unexplained should be professionally evaluated rather than repeatedly treated at home.
Home Care While Waiting for Dental Evaluation
Until examined by a dental professional:
-
Brush twice daily with a soft-bristled toothbrush.
-
Clean between the teeth gently with floss or an appropriate interdental cleaner.
-
Do not scrape calculus with metal instruments.
-
Avoid smoking and tobacco products.
-
Limit frequent sugary drinks and snacks.
-
Maintain adequate hydration.
-
Avoid repeatedly touching, squeezing, or traumatizing the lesion.
-
Follow prescribed medications exactly as directed by the treating clinician.
Mouthwash may help with oral hygiene in selected circumstances, but it does not remove established calculus and should not be used to delay evaluation of a persistent lesion.
Frequently Asked Questions
1. Can lower-teeth calculus cause a lump under the tongue?
Not necessarily. Calculus can cause gum inflammation around the teeth, but a lump or lesion in the floor of the mouth has many possible causes and should be assessed separately.
2. Can heavy calculus cause bleeding gums?
Yes. Plaque and calculus can contribute to gingival inflammation, which commonly causes gums to become red, swollen, and prone to bleeding.
3. Can brushing remove hardened calculus?
No. Brushing can help control plaque, but hardened calculus generally requires professional removal with dental instruments.
4. Is a white spot under the tongue always an infection?
No. White areas in the mouth can have many causes. Appearance alone is not sufficient to determine the diagnosis.
5. How long should I wait for a mouth lesion to heal?
A lesion that persists for approximately 2 weeks or longer should be evaluated by a dentist or doctor, particularly if the cause is unknown.
6. Can a floor-of-mouth lesion be caused by a salivary gland problem?
Yes. The floor of the mouth contains important salivary-gland structures and ducts, so some swellings in this area can be related to salivary-gland conditions.
7. Should I remove the calculus myself?
No. Do not use knives, needles, metal picks, or other sharp objects to remove calculus. Professional scaling is safer.
8. Does removing calculus make a mouth lesion disappear?
Not necessarily. Professional cleaning can improve gum inflammation caused by plaque and calculus, but an independent floor-of-mouth lesion may require its own evaluation.
9. When should I see an oral medicine specialist?
Referral may be appropriate when a lesion is persistent, unexplained, recurrent, unusual in appearance, or does not respond as expected to initial management.
10. Can a dentist diagnose an oral lesion from a photograph?
A photograph can provide useful information, but it cannot reliably establish a diagnosis. A proper examination may include palpation, dental examination, medical history, and sometimes imaging or biopsy depending on the findings.
11. Is a floor-of-mouth lesion always cancer?
No. Many oral lesions are benign or caused by irritation, infection, trauma, or other non-cancerous conditions. However, persistent or suspicious lesions should be professionally evaluated because serious conditions can sometimes present with relatively subtle symptoms.
12. What is the most important next step?
The safest approach is to address the obvious calculus and gum disease while ensuring that any persistent or unexplained floor-of-mouth lesion receives appropriate professional assessment.
Frequently Asked Questions About Lower Teeth Calculus and Floor-of-Mouth Lesions
1. Why does calculus build up so quickly behind the lower front teeth?
The lower front teeth are close to the openings of major salivary ducts. Saliva contains minerals that can help plaque harden into calculus. Individual saliva characteristics, tooth alignment, and plaque-control habits can influence how quickly deposits accumulate.
2. Can lower teeth calculus cause swollen gums?
Yes. Plaque associated with calculus can contribute to gingivitis, causing redness, swelling, and bleeding. If inflammation progresses to periodontitis, the supporting tissues and bone may be damaged. A periodontal examination is needed to determine the severity.
3. Can calculus cause a lump under the tongue?
Calculus on the teeth does not ordinarily explain a separate lump on the floor of the mouth. A salivary duct stone, ranula, traumatic lesion, infection, or another soft-tissue condition may be responsible. A dentist should examine the lesion rather than assuming it is caused by tartar.
4. How do dentists remove hard calculus from the lower front teeth?
A dentist or appropriately trained dental professional removes calculus using professional scaling instruments, which may include ultrasonic scalers and hand instruments. Deeper deposits associated with periodontitis may require subgingival instrumentation or scaling and root planing.
5. Can I remove calculus at home using a metal tool?
No. Hardened calculus cannot be safely and reliably removed at home using improvised metal instruments. Scraping can injure the gums, damage oral tissues, or cause bleeding. Professional cleaning is the safer approach.
6. Will professional scaling make the floor-of-mouth lesion disappear?
Not necessarily. Scaling treats calculus and helps control plaque-related gum inflammation. A lesion caused by a salivary stone, ranula, trauma, or another condition may need separate management. Improvement after scaling does not replace a proper diagnosis of an unexplained lesion.
7. How long does it take for gums to improve after scaling?
Mild gum inflammation may improve over several days to approximately two weeks when professional treatment is combined with effective daily plaque control. Recovery varies according to the severity of inflammation and the presence of periodontal disease. Persistent symptoms require reassessment.
8. Is a floor-of-mouth lesion always cancerous?
No. Many oral lesions are benign or inflammatory. Nevertheless, an unexplained lump, persistent ulcer, firm lesion, red or white patch, or lesion that bleeds without an obvious cause must be evaluated. Suspicious lesions may require biopsy to establish a diagnosis.
9. How long should I wait before having a mouth lesion checked?
Arrange an examination promptly for an unexplained lesion instead of waiting for it to disappear. Current American Dental Association guidance emphasizes timely reassessment of persistent or suspicious lesions; if a lesion remains unresolved after 10–14 days of initial evaluation without a definitive diagnosis and treatment plan, biopsy or specialist referral may be appropriate. Seek assessment sooner if the lesion is suspicious or worsening.
10. Can a salivary stone develop beneath the tongue?
Yes. A stone can obstruct a salivary duct in the floor of the mouth. Symptoms may include intermittent swelling or pain that becomes more noticeable during meals. A dentist or appropriate medical specialist can determine whether imaging or removal is necessary.
11. Do I need antibiotics for lower teeth calculus or a mouth lesion?
Antibiotics are not routinely required for calculus or uncomplicated plaque-related gingivitis. They are appropriate only for selected infections and clinical circumstances. A suspected abscess or spreading infection needs professional assessment and treatment of the underlying cause; antibiotics alone may not resolve it.
12. When is a floor-of-mouth lesion an emergency?
Seek emergency care immediately if swelling rapidly increases, the tongue is pushed upward, or breathing or swallowing becomes difficult. Fever with worsening swelling, pus, or significant pain also warrants urgent assessment.
13. Can a dentist diagnose a floor-of-mouth lesion by looking at it?
A clinical examination provides important clues, but appearance alone may not establish the diagnosis. Depending on the lesion, the clinician may recommend palpation, imaging, specialist evaluation, or biopsy with laboratory examination of the tissue.
14. What is the best way to prevent calculus from returning?
Brush twice daily with fluoride toothpaste, clean between the teeth daily, and attend professional dental cleanings at an interval recommended for your periodontal condition. Patients who accumulate calculus rapidly or have periodontal disease may need more frequent professional maintenance.
Important Medical Disclaimer
This information is for general educational purposes and is not a diagnosis or substitute for an in-person examination. The appearance of calculus, gum inflammation, or a floor-of-mouth lesion can vary considerably between individuals. A qualified dentist, oral medicine specialist, oral and maxillofacial surgeon, or physician should determine the diagnosis and appropriate treatment.
If swelling is interfering with breathing or swallowing, seek emergency medical care rather than waiting for a routine dental appointment.
Final Clinical Comment
The strongest photographic finding is calculus accumulation on the lower teeth with possible gingival inflammation.
The photograph does not establish the presence or severity of periodontitis because bone loss and clinical attachment loss cannot be determined reliably from this image.
The circled floor-of-mouth area is a separate finding and requires direct examination. It may represent normal salivary or anatomical tissue, but other causes cannot be excluded from a photograph.
A comprehensive periodontal examination followed by appropriate professional scaling is the logical next step. If periodontal disease is confirmed, scaling and root planing may be required. The first 14 days can show improvement in inflammation, but established periodontal disease generally requires longer-term monitoring and maintenance.
This case should therefore be classified as a preliminary photographic dental assessment rather than a definitive diagnosis.
Related Clinical Cases
Patients with lower front gum inflammation may also experience tartar buildup, periodontal disease, gum abscesses, or tooth decay. Explore these related clinical case studies.