Modern Dentistry, Timeless Smiles.

Child Dental Case: Multiple Tooth Decay Concerns — 100% Zoom Analysis, 14-Day Treatment Plan & Prevention
Image:
Severity:
Teeth Problems:
Multiple Tooth Decay in Children: Expert Case Analysis, Treatment Priorities, and a 14-Day Prevention Plan
1. Clinical Overview: Why Multiple Cavities Require Attention
When a child develops tooth decay in several teeth, the condition should be evaluated as a broader oral-health problem rather than as a collection of unrelated cavities.
Dental caries is a multifactorial disease involving plaque bacteria, frequent exposure to fermentable carbohydrates, susceptible tooth surfaces, and insufficient protective factors such as fluoride and saliva. A child may develop several cavities when these risk factors persist over time.
Common contributing factors include:
-
Frequent consumption of sweets, biscuits, candy, sweetened drinks, and other sugary snacks.
-
Repeated sipping of juice or sweetened beverages throughout the day.
-
Inadequate brushing with fluoride toothpaste or insufficient parental supervision.
-
Plaque accumulation around the gumline and in the grooves of molars.
-
Deep pits and fissures that retain food debris and plaque.
-
Previous cavities, which indicate an increased risk of future decay.
-
Limited access to preventive dental care.
Clinical principle: Multiple cavities do not automatically mean that every affected tooth requires extraction. Each tooth must be assessed according to the extent of decay, the condition of the dental pulp, the presence of infection, and whether the tooth can be predictably restored.
2. Understanding the Stages of Tooth Decay
The treatment approach depends on how far the carious lesion has progressed.
Stage 1: Early enamel demineralization
Early decay may appear as a white, chalky area on the tooth surface. At this stage, the enamel may still be intact.
Possible management: Fluoride-based preventive care, improved plaque removal, dietary modification, and professional monitoring. Some early lesions can remineralize, but treatment depends on their activity and location.
Stage 2: Decay extending into dentin
Once the lesion progresses through the enamel into dentin, the tooth may develop a visible cavity. The child may experience sensitivity to cold, sweets, or chewing.
Possible management: A restoration may be required. Some lesions can be managed with minimally invasive or non-restorative approaches in appropriately selected cases, but a cavitated lesion needs professional assessment.
Stage 3: Deep decay approaching the dental pulp
The pulp contains the nerves and blood vessels inside the tooth. Deep decay can cause inflammation, resulting in pain that may linger after exposure to hot or cold foods.
Possible management: Depending on the pulp diagnosis, a dentist may consider selective caries removal and vital pulp treatment, a pulpotomy, or another appropriate procedure. The choice differs between primary teeth and permanent teeth.
Stage 4: Pulp infection or dental abscess
Advanced decay can lead to pulp death and infection around the tooth roots. Symptoms may include spontaneous pain, pain during chewing, gum swelling, or a draining sinus.
Possible management: Urgent dental assessment is necessary. Treatment may involve root canal treatment or an appropriate pulp procedure, or extraction when the tooth cannot be predictably saved. Antibiotics alone do not remove the source of infection.
The clinical recommendations above are consistent with the American Academy of Pediatric Dentistry's guidance on pediatric restorative dentistry and pulp therapy.
3. Expert Dental Case Assessment: What Should Be Examined?
When a child presents with multiple decayed teeth, the examination should establish the severity of disease and identify the teeth that need treatment first.
A. Clinical examination
The dentist should assess:
-
The number and location of affected teeth.
-
Whether the lesions are early, cavitated, or extensive.
-
Plaque accumulation, gum condition, and oral hygiene.
-
Pain history, including spontaneous pain and night waking.
-
Swelling, drainage, tenderness, or other signs of infection.
-
The child's age and whether the affected teeth are primary or permanent.
B. Appropriate dental radiographs
Dental X-rays may be indicated to identify decay between teeth, assess the depth of lesions, and evaluate the surrounding tissues when clinically necessary. The type and number of images should be individualized according to the child's age, examination findings, and diagnostic needs.
C. Caries-risk assessment
A comprehensive assessment should also identify why decay is occurring and which preventive measures are most likely to reduce future lesions.
The dentist may review the child's brushing technique, fluoride exposure, frequency of sugar intake, previous cavities, saliva-related concerns, and access to regular dental care.
Important: Photographs or zoomed images can help document visible changes, but they cannot reliably establish the full depth of a cavity or determine the health of the pulp. Clinical examination and appropriate radiographs may be necessary.
4. A Practical 14-Day Treatment and Prevention Plan
This 14-day schedule is a framework for organizing care. It is not a fixed clinical protocol, and it must not delay urgent treatment or imply that established cavities will heal within two weeks.
Days 1–2: Arrange the dental examination
-
Book a pediatric dentist or a dentist experienced in treating children.
-
Document the child's symptoms and the teeth that appear affected.
-
Report any spontaneous pain, night waking, swelling, fever, or difficulty eating.
-
Establish which teeth need urgent intervention and which lesions can be managed preventively.
If facial swelling, fever associated with dental infection, or rapidly worsening symptoms are present, seek urgent assessment rather than waiting for the planned schedule.
Days 3–4: Begin individualized treatment
Follow the dentist's treatment priorities. Depending on the findings, treatment may include:
-
Fluoride varnish for appropriate lesions and risk levels.
-
Sealants for suitable susceptible pits and fissures.
-
Silver diamine fluoride (SDF) for selected lesions when appropriate and available.
-
Fillings or other restorations for cavitated teeth.
-
Pulp treatment or extraction when indicated by the tooth's condition.
SDF can arrest certain carious lesions, but it permanently darkens the treated decayed tissue and does not restore the tooth's original shape. It is not suitable for every lesion, particularly when urgent treatment of pulpal disease or infection is required.
Days 5–7: Establish a consistent home-care routine
Parents should supervise brushing twice daily using fluoride toothpaste in an age-appropriate amount.
-
Under 3 years: use a smear no larger than a grain of rice.
-
Ages 3–6 years: use a pea-sized amount.
-
Older children: use an appropriate amount of fluoride toothpaste and supervise until brushing is effective.
Encourage the child to spit out toothpaste rather than swallow it. A dentist can advise on additional fluoride measures according to the child's age and caries risk.
Reduce the frequency of sugary snacks and drinks. Offer water between meals and establish regular meal and snack times.
Days 8–10: Review diet and brushing technique
Parents should check whether plaque is accumulating around the gumline, between teeth, and on the back molars.
For children whose teeth touch, the dentist or caregiver should introduce age-appropriate interdental cleaning.
Review the child's typical daily diet. The frequency of sugar exposure matters, not just the total amount consumed. Frequent sipping and grazing can expose teeth to repeated acid attacks.
Avoid using candy or sweetened drinks as frequent rewards. Do not put a child to bed with a bottle containing juice or other sugary liquids.
Days 11–14: Confirm treatment progress and next steps
The dentist should determine whether the planned treatment has been completed or whether additional appointments are necessary.
Parents should confirm:
-
Which teeth have been treated.
-
Which lesions still require definitive treatment.
-
Whether the child needs further preventive applications or sealants.
-
When the next review should occur.
-
Which daily habits need improvement.
A reduction in sensitivity or pain does not prove that the underlying disease has resolved. Some severely affected teeth may stop hurting after the pulp dies, even while infection develops.
Expected outcome: Within 14 days, the family can establish a treatment plan and improve preventive habits. The time required to complete dental treatment depends on the number of affected teeth, the child's cooperation, the severity of disease, and the procedures required.
5. How Parents Can Prevent New Cavities
Fluoride toothpaste and brushing
Brush for approximately two minutes, morning and night, with fluoride toothpaste. Bedtime brushing is particularly important. Parents should assist young children and check the effectiveness of brushing in older children.
Reduce the frequency of sugar exposure
Limit sugary foods and drinks to mealtimes where possible. Water is the preferred drink between meals. Frequent sugar exposure increases the number of acid attacks on tooth enamel.
Consider professional fluoride and sealants
A dentist may recommend professionally applied fluoride and pit-and-fissure sealants for children at increased risk. These measures reduce risk but do not replace the need to treat established cavities.
Maintain individualized dental follow-up
Children with multiple cavities often need closer follow-up than children at low risk. The appropriate interval depends on their disease activity, treatment status, and preventive needs.
Understand the importance of primary teeth
Baby teeth are important for chewing, speech development, comfort, and maintaining space for developing permanent teeth. Although these teeth eventually fall out, untreated decay can cause pain, infection, and premature tooth loss.
The decision to preserve or remove a primary tooth should be based on its condition, the child's age, the expected time until natural exfoliation, and the effect on the developing dentition.
6. Warning Signs That Require Urgent Dental Care
Parents should seek urgent dental assessment for:
-
Severe or persistent tooth pain.
-
Gum or facial swelling.
-
Pus or a draining sinus near a tooth.
-
Fever accompanied by suspected dental infection.
-
Rapidly worsening pain or swelling.
Emergency warning: Difficulty breathing or swallowing, swelling extending toward the eye or neck, or rapidly spreading facial swelling requires emergency medical care. Do not wait for a routine dental appointment.
Do not use leftover antibiotics, place aspirin directly on a tooth, or attempt to drain an abscess at home. Antibiotics are not routinely indicated for uncomplicated cavities and do not replace definitive dental treatment.
Frequently Asked Questions About Multiple Tooth Decay in Children
1. Why does my child have cavities in several teeth at once?
Multiple cavities usually reflect a combination of factors, such as frequent sugar exposure, plaque accumulation, inadequate fluoride protection, susceptible tooth surfaces, and previous caries. A dentist should assess the child's individual risk factors rather than assuming there is only one cause.
2. Can multiple cavities be treated within 14 days?
Some children can complete several procedures within two weeks, but others require more appointments. The treatment schedule depends on lesion depth, infection, the child's cooperation, and the need for pulp therapy or other procedures. A 14-day prevention plan cannot guarantee that every cavity will be treated or healed during that period.
3. Can tooth decay heal without a filling?
Some early, non-cavitated lesions can arrest or remineralize with appropriate fluoride exposure and plaque control. Once a cavity has formed, however, it may require restoration or another dentist-directed intervention. Home care alone cannot rebuild a substantial area of missing tooth structure.
4. Do baby teeth need treatment if they will eventually fall out?
Yes, when treatment is indicated. Untreated decay can cause pain, infection, difficulty eating, and premature tooth loss. The dentist will determine whether restoration, pulp treatment, monitoring, or extraction is appropriate.
5. Does a dark or black tooth always mean the tooth is infected?
No. Dark discoloration can result from several causes, including arrested decay, staining, trauma, or treatment with silver diamine fluoride. Color alone cannot determine whether the pulp is healthy or infected. A clinical assessment is needed.
6. Is fluoride toothpaste safe for children?
Fluoride toothpaste is recommended for children when used in an age-appropriate amount under adult supervision. Excessive swallowing over time can increase the risk of dental fluorosis in developing teeth. Parents should dispense the correct amount and store toothpaste safely.
7. Should my child take antibiotics for multiple cavities?
Not for cavities alone. Antibiotics are reserved for specific situations, particularly when there is spreading infection or systemic involvement, and must be prescribed by a qualified clinician when indicated. The source of a dental infection still requires appropriate dental treatment.
8. Can a dentist save a tooth with deep decay?
Sometimes. If the pulp is healthy or reversibly inflamed, a tooth-preserving procedure may be possible. If the pulp is irreversibly inflamed or necrotic, other pulp treatment or extraction may be needed. The choice depends on the tooth type, examination findings, radiographs, and restorability.
9. What foods should children avoid when they have multiple cavities?
Reduce frequent exposure to candy, biscuits, sweetened beverages, juice, and other foods or drinks containing free sugars. Sticky sweets and repeated snacking can be particularly problematic. The goal is to reduce the frequency of sugar exposure, provide a balanced diet, and encourage water between meals.
10. How often should a child with multiple cavities visit the dentist?
The interval should be based on the child's individual caries risk and treatment needs. Children with active disease may need shorter review intervals than children with low risk. The dentist should set a specific follow-up schedule after the initial assessment.
11. Is brushing alone enough to prevent new cavities?
Brushing with fluoride toothpaste is essential, but it works best alongside reduced sugar frequency, effective interdental cleaning when appropriate, professional preventive care, and regular risk-based dental reviews.
12. When should parents seek a pediatric dentist?
A pediatric dentist is especially helpful when a young child has multiple cavities, extensive decay, dental anxiety, or complex treatment needs. A general dentist experienced in pediatric care can also provide appropriate assessment and treatment.
Clinical Conclusion
Multiple tooth decay in children is a manageable condition when the disease is identified early and treatment is combined with consistent prevention.
The priority is to determine which teeth can be preserved, which lesions require restorative treatment, and whether any tooth has developed pulpal disease or infection. A structured 14-day plan can help parents organize appointments and establish better daily habits, but it must complement—not replace—professional dental care.
Early intervention, fluoride-based prevention, reduced sugar frequency, and individualized follow-up give children the best opportunity to preserve their teeth and reduce the risk of future cavities.
Medical note: This educational case discussion does not establish a diagnosis for an individual child. Treatment decisions require examination by a qualified dentist, with appropriate imaging when indicated.
Clinical References
-
American Academy of Pediatric Dentistry (AAPD). Caries-risk Assessment and Management for Infants, Children, and Adolescents.
-
AAPD. Pulp Therapy for Primary and Immature Permanent Teeth.
-
American Dental Association (ADA). Caries Prevention and Risk Management.
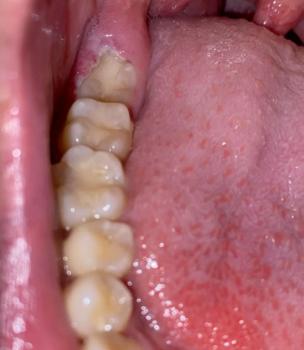
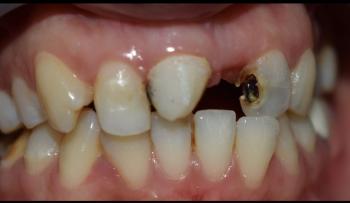
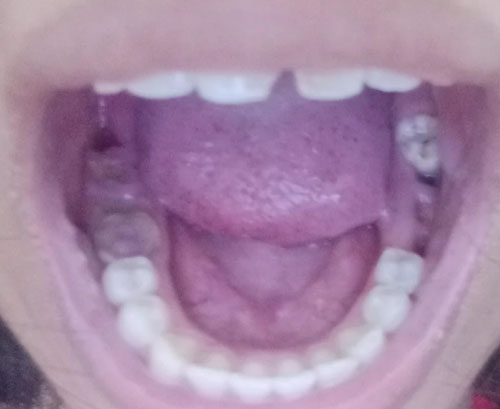
I enlarged the image and examined the visible teeth individually. This is not a definitive diagnosis because the photo is blurred and does not show X-rays, tooth surfaces from all angles, or the child’s symptoms/age. A dentist needs an in-person examination and likely radiographs before deciding whether teeth are restorable.
What stands out
| Area | Visual finding | Concern |
|---|---|---|
| Lower right posterior | A dark/gray posterior tooth with an irregular chewing surface | High suspicion of significant caries/cavitation |
| Lower left posterior | Posterior tooth appears darker/structurally compromised | Possible caries |
| Upper posterior areas | At least one posterior tooth appears discolored/irregular | Possible decay or heavily restored/erupting tooth |
| Lower front teeth | Several teeth appear relatively intact and aligned | No obvious major cavitation visible from this view |
| Gums | Generally pink; no obvious large abscess or dramatic facial swelling visible | Does not rule out infection underneath a tooth |
| Overall | Posterior teeth are the principal concern | Needs a pediatric dental assessment rather than simply cleaning |
Most likely clinical issue
The strongest visual concern is multiple posterior dental caries, with at least one tooth potentially having progressed substantially. I would classify this as needs prompt dental examination, rather than waiting for symptoms to become severe.
Untreated childhood caries can progress to pain, infection, difficulty eating and sleep disruption; once tooth structure is destroyed, it does not simply regenerate.
Important: I would not diagnose an abscess, pulp death, or gum disease from this photograph alone. Those require clinical testing and, when indicated, X-rays.
What could "scale up" if nothing is done for 14 days?
The concern is not that exactly 14 days will cause a predictable change—the rate varies by tooth and depth of decay.
A progression could look like:
Cavity → deeper dentin involvement → pulp inflammation → severe toothache → pulp necrosis/infection → abscess/swelling
If decay has already reached the pulp, simply waiting 14 days can allow symptoms or infection to develop. Pediatric dental guidance recognizes pain, infection and facial swelling as conditions requiring timely evaluation.
A reasonable 14-day plan
Day 0–2 — Examination
- Pediatric dentist examination.
- Determine whether the suspicious posterior teeth are primary or permanent teeth.
- Bitewing/periapical X-rays if clinically indicated.
- Assess whether each affected tooth is restorable.
- Check for pulp involvement, abscess, eruption status and developing permanent teeth.
Days 1–7 — Control the active disease
- Professional cleaning where appropriate.
- Fluoride prevention.
- Restore cavities that can be restored.
- If a primary tooth has deep decay/pulp involvement, the dentist may consider appropriate pulp therapy or extraction depending on restorability and the developing successor. AAPD guidance recognizes pulp therapy or extraction among treatments for odontogenic infections in children.
Days 7–14 — Stabilization and prevention
- Recheck painful/infected teeth.
- Complete remaining urgent treatment.
- Establish daily brushing with fluoride toothpaste and appropriate interdental cleaning.
- Reduce frequent sugary snacks/drinks.
- Establish regular pediatric dental follow-up.
Fourteen days is a reasonable stabilization window, not a guaranteed "healing time." A cavity that has lost tooth structure will generally require dental treatment; it cannot be expected to disappear through brushing alone.
When this becomes urgent
Don't wait 14 days if the child develops:
- facial or cheek swelling
- gum swelling or a pus-filled bump
- fever or significant malaise
- rapidly increasing tooth pain
- difficulty swallowing
- difficulty breathing
- inability to eat/drink because of pain
Significant facial swelling, infection and severe dental pain are recognized pediatric dental emergencies/urgent conditions.
Antibiotics are not automatically the treatment for a cavity. For many dental infections, definitive dental treatment is the priority; antibiotics are generally reserved for situations such as systemic involvement or particular clinical circumstances determined by the dentist.
Accurate Medical Guidance
Important: Children with multiple areas of tooth decay should be evaluated by a dentist, preferably a pediatric dentist. Treatment depends on the child’s age, which teeth are affected, the depth of decay, symptoms, oral hygiene, diet, and whether the teeth are primary (baby) or permanent.
A close-up or “zoom” examination can help illustrate visible problems such as discoloration, plaque accumulation, cavities, fractured tooth structure, or gum irritation. However, a photograph or visual inspection alone cannot determine how deep a cavity is. Dental X-rays may be needed to identify decay between teeth or determine whether the pulp (nerve) is involved.
What Parents Should Know About Multiple Tooth Decay
When a child has several decayed teeth, the goal is not simply to treat the cavities that are already visible. The dentist should also identify why the decay is occurring and how to prevent new lesions.
Common contributing factors include:
- Frequent consumption of sugary foods or drinks
- Juice, sweetened milk, soda, or other sugary beverages
- Frequent snacking throughout the day
- Inadequate brushing or difficulty cleaning certain areas
- Plaque buildup
- Lack of fluoride exposure
- Tooth anatomy or enamel defects
- Previous dental decay
- Certain medical or developmental factors
Do not assume that a painful tooth is the only tooth that needs treatment. Early decay can sometimes cause little or no pain.
Example 14-Day Dental Care Plan
A 14-day plan can be used as a short-term prevention and appointment-preparation routine, but it should not replace professional treatment.
Days 1–3
- Arrange a dental examination.
- Begin consistent twice-daily brushing with fluoride toothpaste appropriate for the child's age.
- Supervise brushing when necessary.
- Reduce frequent sugary snacks and drinks.
- Encourage water between meals.
Days 4–7
- Continue twice-daily brushing.
- Clean between teeth where appropriate.
- Keep sugary foods and drinks mainly with meals rather than frequent snacking.
- Follow any treatment instructions provided by the dentist.
Days 8–14
- Maintain the same oral-hygiene routine.
- Attend the scheduled dental appointment.
- Complete recommended fillings or other treatment rather than waiting for symptoms to worsen.
- Ask the dentist about fluoride varnish, sealants, dietary changes, and an appropriate recall schedule.
Important: A cavity does not normally disappear simply because brushing improves. Very early enamel changes may sometimes be arrested or remineralized with appropriate preventive care, but an established cavity with structural loss generally requires professional treatment.
When to Seek Urgent Dental Care
Parents should seek prompt dental evaluation if a child develops:
- Facial or jaw swelling
- Swelling around the gums
- Fever associated with dental symptoms
- Severe or persistent toothache
- Pus or drainage
- Difficulty opening the mouth
- Difficulty swallowing
- Difficulty breathing
- Significant facial swelling
Difficulty breathing or swallowing, rapidly increasing facial swelling, or a seriously ill-looking child requires urgent medical attention.
Expert Dental Guidance: What Parents Should Know About Multiple Tooth Decay in Children
Multiple areas of tooth decay in a child should be evaluated by a dentist as soon as possible. Decay can progress beneath apparently intact enamel, and a visual photograph alone cannot determine how deep a cavity is or whether the dental pulp is involved.
A dentist will typically assess the child's teeth, gums, symptoms, oral hygiene, dietary habits, fluoride exposure, and previous history of cavities. Dental X-rays may be recommended when they are clinically necessary to identify decay between teeth or evaluate the depth and extent of disease.
Can multiple cavities be treated within 14 days?
A 14-day period can be useful as a short-term treatment and prevention phase, but it should not be presented as a guaranteed time in which all cavities will heal.
Treatment depends on the number, location, and severity of the lesions.
Early tooth decay that has not formed a cavity may sometimes be managed with preventive measures such as fluoride treatment, improved plaque control, and dietary changes. A cavity that has already caused structural damage generally requires restorative dental treatment rather than simply waiting for it to heal.
If decay has reached the pulp, the treatment may be more extensive. Depending on the child's age, the affected tooth, and the condition of the tooth, the dentist may consider pulp therapy, a restoration, or extraction when the tooth cannot be predictably saved.
What should parents do first?
The priority is to arrange a dental examination rather than attempting to determine the severity of every cavity at home.
Parents can help by:
-
Brushing the child's teeth twice daily with fluoride toothpaste appropriate for the child's age.
-
Helping or supervising brushing so all tooth surfaces are cleaned.
-
Cleaning between teeth when the spaces are closed or when the dentist recommends interdental cleaning.
-
Reducing frequent exposure to sugary foods and drinks.
-
Avoiding prolonged sipping of sweetened beverages.
-
Offering water between meals.
-
Following the dentist's recommended recall and fluoride schedule.
-
Completing prescribed dental treatment rather than treating pain alone.
Can tooth decay stop progressing?
Early non-cavitated lesions can sometimes be arrested or remineralized when the conditions causing mineral loss are controlled. Fluoride is an important part of preventing and managing early caries.
However, a tooth with a significant cavity has already lost tooth structure. It should not be assumed that brushing or dietary changes alone will rebuild the missing structure.
Why are children particularly vulnerable to tooth decay?
Children may have increased caries risk because of frequent sugar exposure, inadequate plaque removal, limited fluoride exposure, enamel vulnerability, orthodontic appliances, dry mouth, developmental factors, or other individual circumstances.
The important issue is not simply the amount of sugar eaten on one occasion. How frequently teeth are exposed to fermentable carbohydrates throughout the day also matters.
When should parents seek urgent dental care?
A child should receive prompt dental evaluation for:
-
Persistent or spontaneous toothache
-
Pain that wakes the child at night
-
Facial or jaw swelling
-
Gum swelling or a dental abscess
-
Fever associated with a suspected dental infection
-
Difficulty chewing because of dental pain
-
A broken or severely weakened tooth
Difficulty breathing or swallowing, rapidly increasing facial or neck swelling, or a child who appears seriously unwell requires urgent medical attention.
Dentist-Expert Perspective
A dentist's role is not simply to identify cavities. The goal is to determine why the disease is occurring, how active it is, which teeth require treatment, and how future disease can be prevented.
For a child with multiple areas of decay, a comprehensive plan may include:
-
Clinical examination – evaluating teeth, gums, plaque, symptoms, and visible lesions.
-
Risk assessment – reviewing diet, fluoride exposure, oral hygiene, previous caries, and other risk factors.
-
Radiographs when indicated – particularly when decay may be hidden between teeth or when the depth of a lesion needs assessment.
-
Disease-control measures – improving brushing, fluoride exposure, diet, and plaque control.
-
Restorative treatment when necessary – repairing teeth that have developed cavities.
-
Follow-up – monitoring whether early lesions have arrested and ensuring completed restorations remain healthy.
-
Prevention – establishing a sustainable home-care routine and appropriate dental recall schedule.
The best treatment plan is individualized. A child should not receive invasive treatment solely because a photograph appears concerning, and a parent should not delay professional assessment because a tooth does not currently hurt.
Frequently Asked Questions
1. Can multiple cavities in a child be treated?
Yes. Treatment depends on the severity and location of the decay. Options can include fluoride treatment for early lesions, fillings, crowns for extensively damaged primary teeth, pulp therapy when the pulp is affected, or extraction when a tooth cannot reasonably be restored.
2. Can baby teeth be ignored because they eventually fall out?
No. Primary teeth help children chew, speak, and maintain appropriate space for developing permanent teeth. Untreated decay can cause pain, infection, difficulty eating, and other complications.
3. Can brushing remove an existing cavity?
Brushing helps prevent progression and can support remineralization of very early enamel lesions. However, it cannot rebuild a tooth after a significant cavity has formed.
4. Does every cavity require a filling?
Not necessarily. Very early lesions may sometimes be managed with preventive treatment and monitoring. A dentist must determine whether a lesion is cavitated and how advanced it is.
5. Does a child need dental X-rays?
Sometimes. X-rays can reveal decay that cannot be seen directly, particularly between teeth, and can help assess the extent of disease. The dentist determines whether an X-ray is necessary based on the child's individual risk and examination.
6. Is sugar the only cause of tooth decay?
No. Tooth decay results from interactions between oral bacteria, fermentable carbohydrates, tooth surfaces, saliva, and time. Frequent exposure to sugary or carbohydrate-containing foods and drinks can increase risk.
7. Is fruit juice healthy for a child’s teeth?
Even 100% fruit juice contains naturally occurring sugars and can contribute to tooth decay when consumed frequently. Water is generally the better everyday drink for dental health.
8. Should a child brush immediately after eating?
A consistent twice-daily fluoride-toothpaste routine is more important than trying to brush after every meal. After acidic foods or drinks, waiting before brushing can help avoid brushing softened enamel.
9. Can dental decay spread from one tooth to another?
Decay does not literally “jump” from one tooth to another. However, the same oral environment—plaque, frequent sugar exposure, and inadequate fluoride protection—can cause multiple teeth to develop decay.
10. What should parents do if the child has tooth pain?
Arrange a dental examination rather than relying only on pain medicine. Pain can indicate inflammation, infection, or advanced decay.
11. Can cavities be prevented from coming back?
The risk can be substantially reduced through fluoride toothpaste, effective plaque removal, limiting frequent sugar exposure, regular dental care, and preventive treatments recommended by the dentist.
12. Is a 14-day treatment plan enough to cure multiple cavities?
Not necessarily. Fourteen days is better described as a short-term action and prevention plan. The actual treatment may require several dental visits and depends on the condition of each affected tooth.
13. Should parents wait until a child has pain before visiting the dentist?
No. Early decay can be painless. Regular examinations allow problems to be detected before they become more extensive.
14. Who should evaluate a child with extensive tooth decay?
A general dentist experienced in treating children can provide care, while a pediatric dentist may be particularly appropriate for young children, extensive decay, dental anxiety, special healthcare needs, or complex treatment.
Medical disclaimer: This information is for general education and does not diagnose or treat an individual child. A dentist must examine the child to determine the appropriate diagnosis and treatment plan.
About the child's comment
“My mother works abroad when I was a child and my father is an alcoholic so he doesn't pay attention to me.”
That history is important context, but it should not be interpreted as proof that the child or parent is responsible for the dental condition. Limited supervision, disrupted caregiving, diet, access to dental care and many other factors can contribute to untreated childhood dental disease.
The most constructive approach is nonjudgmental care: stabilize the child's oral health first, then establish a reliable dental home and prevention routine.
Bottom line
Visual priority: HIGH — posterior teeth require professional assessment soon.
The image suggests multiple areas suspicious for dental decay, but the depth and whether the pulp is infected cannot be determined from this photograph.
Related Clinical Cases
Patients with lower front gum inflammation may also experience tartar buildup, periodontal disease, gum abscesses, or tooth decay. Explore these related clinical case studies.