Healthy Teeth, Happy Life.

Severe Tartar on Lower Front Teeth: Hidden Gum Disease, Bone Loss Risk, Treatment Process & 14-Day Healing Timeline
Image:
Severity:
Teeth Problems:
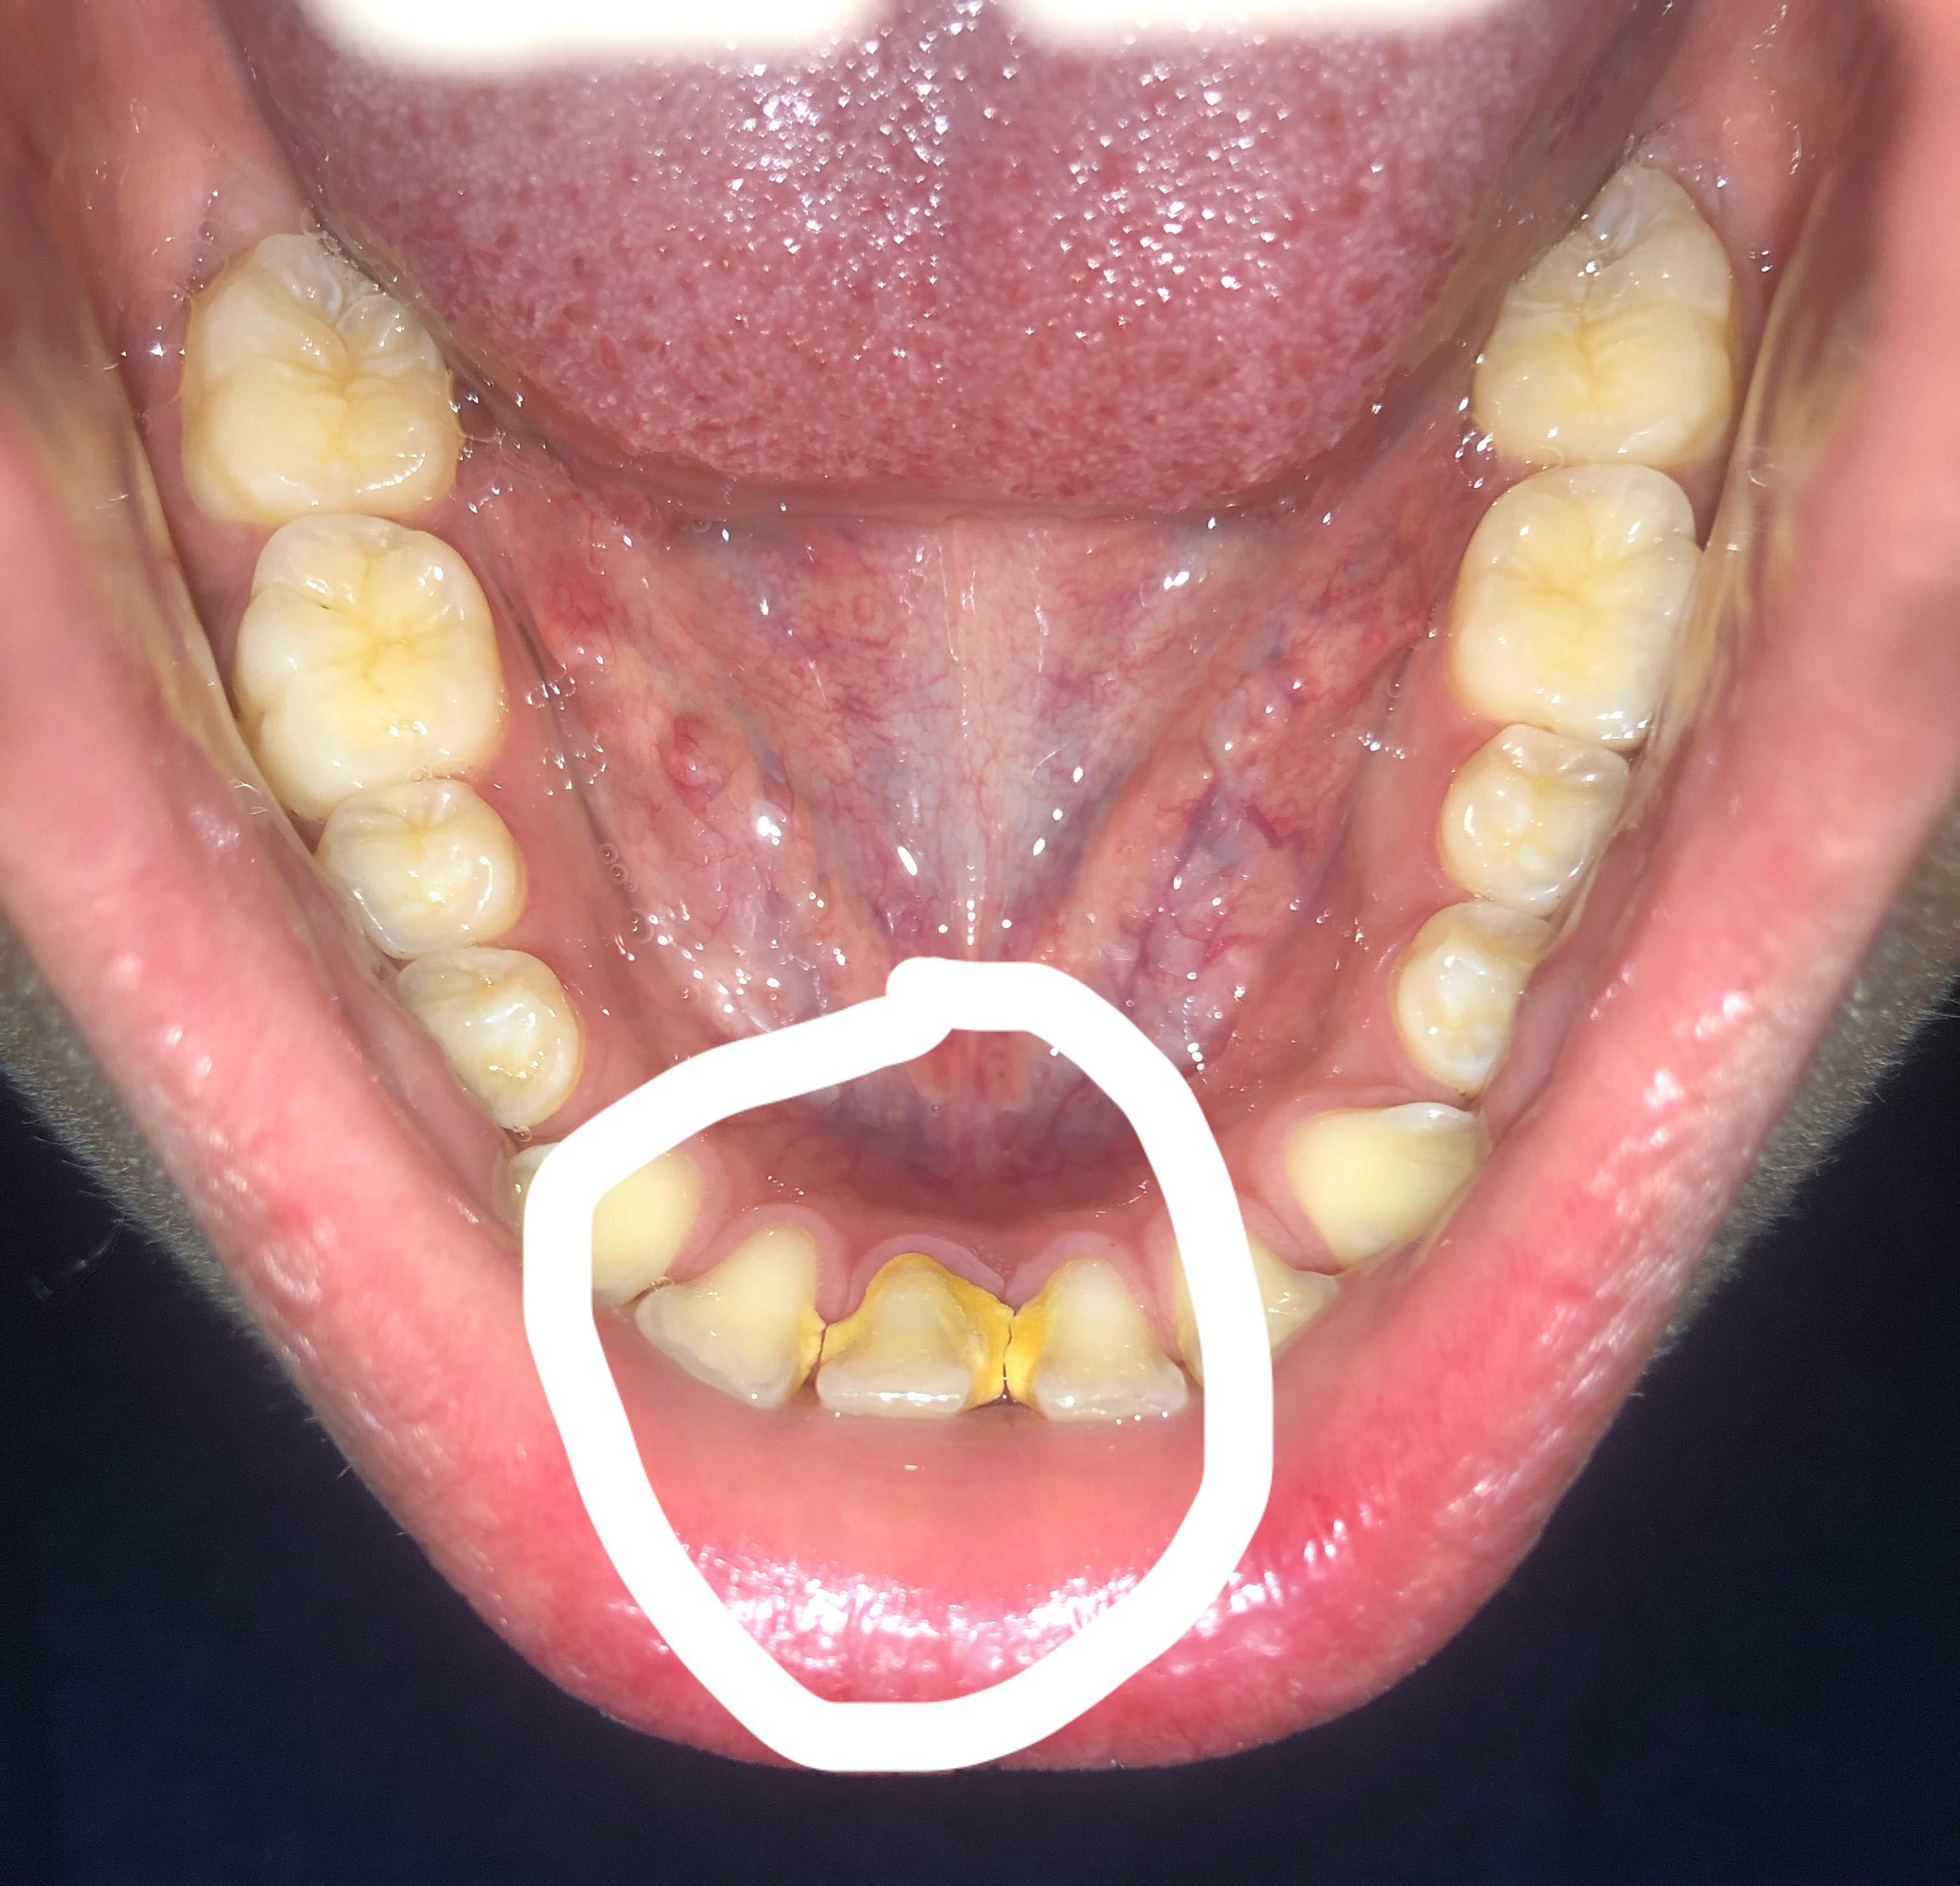
I examined the photograph at 100% resolution and focused especially on the circled lower-front region. This is a clinical-photo assessment, not a definitive diagnosis; periodontal probing and appropriate X-rays are needed to determine whether there is bone or attachment loss.
Overall impression
The circled lower anterior teeth have a very heavy, hard-looking calculus/tartar deposit, especially around the gumline and between the lower incisors. The teeth are also noticeably crowded/rotated, which creates plaque-retentive areas.
The most important question is whether this is severe gingivitis only or whether it has progressed to periodontitis with periodontal pockets and bone loss. A photograph cannot establish that distinction. NIDCR notes that periodontal diagnosis requires gum measurements/probing, tooth examination and, when indicated, X-rays to evaluate bone loss.
Visual assessment
| Finding | My assessment from the photo |
|---|---|
| Lower anterior calculus | Very heavy |
| Plaque retention | High |
| Lower incisor crowding/rotation | Moderate–severe |
| Gingival inflammation | Likely present |
| Gum recession | Possible; needs clinical measurement |
| Periodontal pockets | Cannot determine photographically |
| Bone loss | Cannot determine photographically |
| Abscess/pus | No obvious abscess visible |
| Obvious emergency | Not apparent from this photograph |
The circled teeth
The central lower teeth appear to have large yellow/brown mineralized deposits extending along the cervical/interproximal surfaces. Some of what appears to be tooth structure may actually be calculus, so I would not assume that all of the visible yellow material represents damaged tooth.
The crowding is important because the overlapping surfaces are difficult to clean. Plaque that remains can mineralize into calculus, and calculus cannot be removed effectively by brushing or flossing; professional instruments are required.
Could this already be periodontitis?
Possibly, but I would not label it periodontitis from this photograph alone.
The dentist should measure periodontal pockets around every lower anterior tooth. Healthy pockets are generally around 1–3 mm; deeper pockets can indicate periodontal disease. X-rays can then determine whether supporting bone has been lost.
If there is attachment/bone loss, the treatment becomes more than a routine cleaning.
What I would do
Stage 1 — Examination
At the first appointment:
- Full dental examination
- Periodontal charting/probing
- Check bleeding on probing
- Check mobility of the lower incisors
- Evaluate gum recession
- Evaluate the amount and location of calculus
- Take appropriate dental radiographs if periodontal disease is suspected
- Determine whether this is gingivitis or established periodontitis
Stage 2 — Remove the calculus
If there is no significant attachment loss, professional scaling/debridement may be sufficient.
If periodontal pockets and attachment loss are found, the dentist may recommend scaling and root planing (SRP). ADA guidance describes SRP as a treatment for periodontal disease involving removal of plaque/calculus from tooth and root surfaces below the gumline.
Do not attempt to scrape this calculus off at home with metal instruments.
Stage 3 — Re-evaluation
After treatment, the dentist should reassess:
- inflammation
- bleeding
- pocket depths
- tooth mobility
- gum position
- remaining calculus
- patient's home-care technique
If deeper pockets remain, additional periodontal treatment may be necessary.
Severe Tartar Behind the Lower Front Teeth: Treatment, Gum Recession, and Bone Loss Prevention
Why Severe Tartar on the Lower Front Teeth Needs Professional Attention
Heavy tartar buildup behind the lower front teeth is a common dental finding. This area is particularly prone to mineralized plaque accumulation because saliva from the nearby salivary glands can contribute minerals that harden plaque on the tooth surfaces.
Tartar, also called dental calculus, cannot be safely removed with ordinary brushing once it has hardened. Its rough surface can retain additional plaque, increasing the difficulty of maintaining healthy gums.
Expert clinical insight: The amount of visible tartar does not reliably indicate the severity of periodontal disease. A patient may have substantial calculus with gingivitis but no bone loss, while another patient with less visible buildup may already have periodontitis. The diagnosis depends on gum measurements, attachment levels, tooth mobility, and, when indicated, dental X-rays.
What Happens Beneath Severe Tartar Buildup?
The disease process usually begins when bacterial plaque accumulates along the gumline. If it is not removed effectively, some plaque hardens into calculus. The resulting plaque-retentive surfaces make gum inflammation more difficult to control.
There are two important clinical conditions to distinguish:
1. Gingivitis: Gum Inflammation Without Supporting Bone Loss
Common findings include:
-
Red or swollen gums around the lower incisors.
-
Bleeding during brushing or flossing.
-
Tenderness and persistent bad breath.
-
Plaque and tartar accumulation near the gumline.
Gingivitis can generally be reversed with effective plaque control and professional cleaning. However, untreated inflammation may progress to periodontitis in susceptible individuals.
2. Periodontitis: Damage to the Supporting Tissues
Periodontitis affects the tissues that anchor the teeth. The gums may recede, periodontal pockets may deepen, and the supporting bone may be lost.
Possible warning signs include:
-
Gum recession that makes the teeth appear longer.
-
Spaces developing between teeth.
-
Persistent bleeding or gum inflammation.
-
Teeth that feel loose or have changed position.
-
Food becoming trapped between previously close teeth.
Periodontitis can progress with relatively little pain. Therefore, the absence of toothache does not exclude significant periodontal damage.
How a Dentist Evaluates Severe Lower Front Tartar
A comprehensive examination is more informative than judging the teeth from a photograph alone.
Step 1: Clinical examination
The dentist assesses the amount and location of calculus, gum inflammation, recession, tooth mobility, and any other dental problems.
Step 2: Periodontal pocket measurements
A periodontal probe measures the spaces between the teeth and gums. Deeper pockets can indicate periodontal disease, but the measurements must be interpreted alongside gum recession, bleeding, and attachment loss.
Step 3: Dental X-rays when indicated
Appropriate X-rays help assess the bone supporting the lower front teeth. They can reveal bone loss that is not visible during an ordinary visual inspection.
Step 4: Individualized diagnosis
The dentist determines whether the patient needs routine professional cleaning, periodontal deep cleaning, further periodontal treatment, or referral to a periodontist.
Severe Tartar Lower Front Teeth Treatment Process
Stage 1: Professional Scaling
The dentist or dental hygienist uses appropriate instruments to remove hardened calculus from above the gumline and, when accessible and indicated, beneath it.
Ultrasonic instruments and hand scalers may be used. The choice depends on the patient's needs and the clinician's assessment.
Scaling removes deposits that brushing cannot eliminate. It does not, by itself, rebuild bone already lost to periodontitis.
Stage 2: Scaling and Root Planing When Periodontitis Is Present
If examination confirms periodontal pockets and supporting tissue damage, the dentist may recommend scaling and root planing.
This treatment removes plaque and calculus from affected root surfaces beneath the gums. Local anesthesia may be used to improve comfort, and treatment may be divided across several appointments.
The objective is to reduce inflammation, decrease pocket depths where possible, and create root surfaces that can be maintained with daily oral hygiene.
Stage 3: Reassessment of Gum Health
After treatment, the dentist evaluates bleeding, inflammation, pocket depths, and the patient's plaque-control technique.
Some patients improve sufficiently with nonsurgical treatment and maintenance. Others may require additional periodontal treatment if deep pockets or inaccessible deposits remain.
Stage 4: Long-Term Maintenance
Periodontitis is a chronic condition that requires ongoing management. Once active treatment is complete, the dentist establishes a suitable maintenance schedule based on disease severity, response to treatment, and individual risk factors.
Patients with a history of periodontitis often need periodontal maintenance more frequently than patients who only require routine preventive cleaning.
What to Expect During the First 14 Days After Deep Cleaning
Healing varies according to the extent of inflammation, the type of treatment performed, and the patient's overall health. The following is a general guide, not a guaranteed timetable.
Days 1–2: Early recovery
Mild gum tenderness, slight bleeding, and temporary tooth sensitivity may occur after scaling and root planing. Follow the dentist's aftercare instructions and use a soft-bristled toothbrush.
Days 3–7: Symptoms may begin to settle
Bleeding and tenderness may decrease as inflammation improves. Sensitivity to cold air, cold drinks, or hot drinks can persist for several days and sometimes longer.
Days 8–14: Continued improvement
Many patients notice healthier-looking gums and easier cleaning. However, gum tissues may need several weeks to show their full response to nonsurgical periodontal treatment.
At this stage, the dentist may arrange a follow-up appointment or continue monitoring the response according to the treatment plan.
Important distinction: Fourteen days is not a universal healing deadline. A reduction in bleeding does not prove that all periodontal pockets have resolved, and existing bone loss does not automatically regenerate after tartar removal.
Can Lost Bone Around the Lower Front Teeth Grow Back?
Removing tartar and controlling periodontal inflammation can help preserve the supporting tissues that remain. However, conventional scaling and root planing does not predictably restore bone that has already been destroyed.
Some periodontal defects may be candidates for regenerative procedures, depending on their shape, depth, location, and the patient's overall periodontal condition. A periodontist can assess whether these options are appropriate.
The most important first step is to control active disease and prevent further damage.
How to Prevent Severe Tartar From Returning
-
Brush twice daily with fluoride toothpaste and a soft-bristled toothbrush.
-
Clean between the teeth every day using floss or appropriately sized interdental brushes.
-
Pay particular attention to the tongue-side surfaces of the lower front teeth.
-
Avoid tobacco products, which can worsen periodontal health and treatment outcomes.
-
Manage diabetes carefully if applicable.
-
Attend professional cleaning and periodontal maintenance appointments as recommended.
-
Do not attempt to scrape hardened calculus off your teeth with metal tools or sharp objects.
Home care removes soft plaque but cannot reliably remove established calculus. Professional assessment is essential when tartar is heavy or the gums are persistently inflamed.
When Should You See a Dentist Urgently?
Arrange a dental assessment promptly if you notice persistent gum bleeding, increasing recession, loose teeth, or continuing swelling.
Seek urgent dental care for significant swelling, pus, severe or worsening pain, or rapidly worsening symptoms. Facial or neck swelling, difficulty swallowing or breathing, or rapidly spreading swelling requires emergency medical attention.
Antibiotics are not a substitute for removing calculus or treating the underlying periodontal problem. Medication should be used only when clinically indicated and prescribed by a qualified professional.
Clinical Takeaway
Severe tartar behind the lower front teeth is a reason to arrange a professional examination, particularly when accompanied by bleeding gums, recession, or tooth mobility. The correct treatment depends on whether the patient has gingivitis, periodontitis, or another dental condition.
Early assessment, appropriate professional cleaning, effective daily plaque control, and regular periodontal maintenance offer the best opportunity to preserve the remaining gum and bone support.
What happens over 14 days?
If the primary problem is gingivitis caused by plaque/calculus, the gums can begin improving after professional removal of the irritants and improved oral hygiene.
A reasonable expectation is:
Day 0: examination + professional cleaning/debridement
Days 1–3: possible tenderness, sensitivity and some bleeding
Days 4–7: inflammation should begin decreasing
Days 7–14: gums may look considerably healthier
Around 2–4 weeks: periodontal reassessment may be appropriate depending on the initial findings
After deep cleaning, ADA notes that discomfort can last a day or two and sensitivity may last up to about a week; the gums can initially remain tender or bleed.
But 14 days does NOT mean the whole problem is healed.
If there is already periodontal bone/attachment loss, 14 days cannot regenerate the lost supporting structures.
The goal of the first 14 days is primarily to reduce the inflammatory burden and establish effective plaque control.
What could "scale up" if treatment is delayed?
This is the progression I would be concerned about:
Heavy calculus
↓
Persistent plaque accumulation
↓
Gingivitis / bleeding gums
↓
Periodontal pocket formation
↓
Attachment loss
↓
Alveolar bone loss
↓
Gum recession / tooth sensitivity
↓
Tooth mobility
↓
Possible tooth loss
NIDCR specifically notes that untreated gum disease can progress from inflamed gums to destruction of the supporting tissues and bone, potentially resulting in loose teeth or tooth loss.
However, waiting 14 days is very different from leaving this untreated for months or years. Periodontitis generally progresses over a much longer timeframe, although the appropriate treatment should not be unnecessarily postponed. NIDCR notes that periodontitis can take months or years to develop.
My concern level
Calculus: HIGH
Plaque-retention/crowding: HIGH
Visible gum inflammation: MODERATE–HIGH
Possible underlying periodontal disease: NEEDS TESTING
Immediate emergency from the photograph: NOT APPARENT
The biggest unknown is bone loss. That cannot be reliably assessed from this photograph.
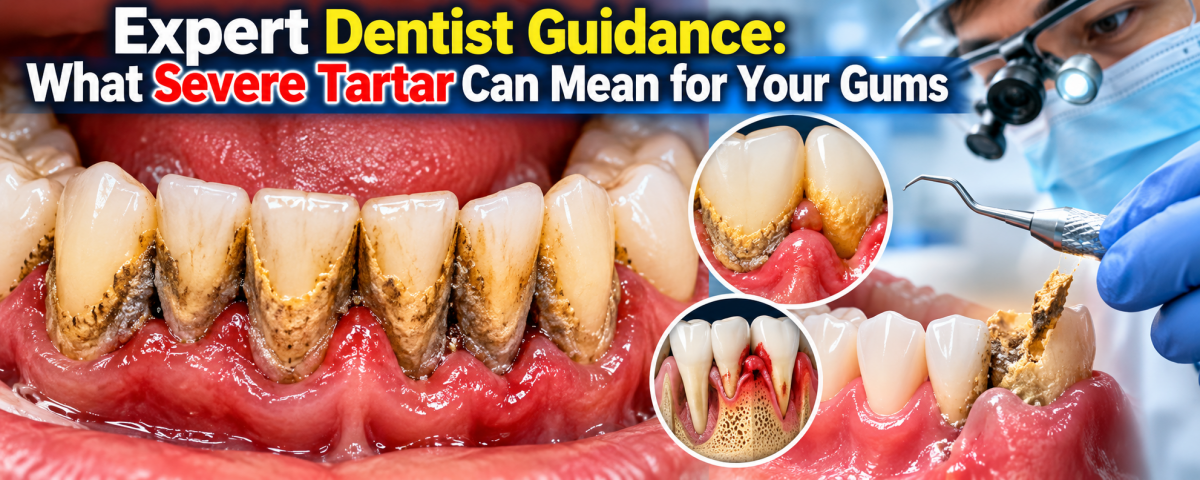
Expert Dentist Guidance: What Severe Tartar Can Mean for Your Gums
Consultant Dentist Perspective
When I see heavy tartar (calculus), particularly around the lower front teeth, my concern is not simply the appearance of the teeth. The more important question is what is happening underneath the gumline.
Tartar is hardened dental plaque. Once plaque mineralizes into calculus, ordinary brushing and flossing cannot reliably remove it. Professional dental instruments are required. Heavy calculus can also make plaque control more difficult and may contribute to persistent gum inflammation.
However, I would not diagnose advanced periodontal disease simply by looking at a photograph. A patient may have severe gingivitis without significant bone loss, while another patient with relatively little visible tartar may already have periodontal pockets and supporting-bone loss.
The Important Clinical Question: Gingivitis or Periodontitis?
The first stage is often gingivitis. The gums may become red, swollen and prone to bleeding.
Gingivitis is generally reversible when the causes of inflammation are addressed through professional care and effective daily plaque control.
Periodontitis is different. It involves destruction of the tissues supporting the teeth and may include periodontal attachment and bone loss. Once bone and attachment have been lost, the condition cannot simply be reversed by brushing; professional periodontal treatment is needed to control the disease.
This is why I would not tell a patient, "You definitely have bone loss," based only on a photograph.
Instead, I would recommend a periodontal examination.
What Should a Dentist Check?
For heavy tartar around the lower front teeth, I would assess:
-
Periodontal pocket depths
-
Bleeding during periodontal probing
-
Gum swelling and inflammation
-
Gum recession
-
Tooth mobility
-
The amount and location of calculus
-
Plaque-retentive areas caused by crowding or rotated teeth
-
The patient's overall periodontal condition
-
Dental X-rays when clinically indicated to evaluate supporting bone
These findings allow the dentist to distinguish uncomplicated gingivitis from established periodontitis and determine the appropriate level of treatment.
Why Lower Front Teeth Commonly Develop Visible Tartar
The lower front teeth are a common location for noticeable calculus deposits because saliva enters the mouth near the openings of the major salivary glands in this region.
Crowded or rotated teeth can make the situation more difficult because some surfaces become harder to clean effectively. This can create areas where plaque remains, eventually mineralizes, and forms calculus.
The presence of crowding does not automatically mean that bone loss has occurred. It means plaque control may be more challenging and the area deserves careful examination.
What Happens During Professional Treatment?
The treatment depends on what the examination shows.
If the problem is mainly gingivitis and supragingival calculus
A dentist or dental hygienist may perform professional scaling and polishing/debridement, followed by individualized oral-hygiene instructions.
The objective is to remove the hardened deposits and reduce the factors that are keeping the gums inflamed.
If periodontitis is diagnosed
Treatment may require more than an ordinary cleaning.
Depending on the periodontal findings, the dentist may recommend scaling and root planing (SRP) or other periodontal treatment. SRP involves professional removal of plaque, calculus and bacterial deposits from tooth and root surfaces, including areas below the gumline. More advanced cases may require periodontal specialist care or surgical treatment.
What Should I Expect After Cleaning?
Patients sometimes become concerned when the gums look different immediately after substantial tartar removal.
Temporary tenderness, sensitivity or minor bleeding can occur after periodontal cleaning. The gums may also appear less swollen as inflammation decreases.
For a case involving primarily gingivitis, improvement may become noticeable over the following days and weeks.
However, I would not promise that every patient will be completely healed in 14 days.
A 14-day period can be useful for observing early improvement in inflammation and oral hygiene, but established periodontitis is a chronic condition requiring ongoing management. Existing bone loss does not regenerate simply because tartar has been removed.
Why You Should Not Scrape Tartar Off Yourself
I strongly discourage patients from trying to remove hard tartar with knives, metal picks, needles or other household instruments.
Improper scraping can injure the gums, damage tooth surfaces or create additional problems without addressing disease beneath the gumline.
Professional cleaning is safer because the clinician can simultaneously evaluate the gums, tooth surfaces, periodontal pockets and other oral-health problems.
What Can Happen If Significant Gum Disease Is Ignored?
Untreated periodontal disease can progress from inflammation to periodontal pocket formation, attachment loss and supporting-bone destruction. Advanced disease can eventually contribute to tooth mobility and tooth loss.
The important point is that not every patient with heavy tartar will develop severe periodontitis.
Risk varies from person to person. Factors associated with more serious periodontal disease include smoking, diabetes, inadequate plaque control and other individual risk factors.
My Practical Recommendation
If you have heavy tartar around the lower front teeth, do not try to diagnose the severity from appearance alone.
Ask your dentist:
"Please check my periodontal pocket depths, bleeding, gum recession and tooth mobility, and determine whether I have any supporting-bone loss. Do I need routine scaling or periodontal treatment such as scaling and root planing?"
That question focuses the appointment on the most important clinical issue: Is this primarily gingivitis, or is there evidence of periodontitis?
When to Seek Urgent Dental Care
Heavy tartar by itself is usually not an emergency.
However, seek prompt dental or medical assessment if you develop:
-
Significant facial or jaw swelling
-
Pus or a suspected dental abscess
-
Fever associated with a dental infection
-
Rapidly increasing swelling or pain
-
Difficulty swallowing
-
Difficulty breathing
-
A rapidly worsening dental infection
Difficulty breathing or swallowing associated with oral/facial swelling can be an emergency and should not be managed by waiting for a routine cleaning appointment.
Frequently Asked Questions
1. Can severe tartar cause gum disease?
Yes. Tartar provides a rough surface that makes plaque accumulation and effective cleaning more difficult. Persistent plaque and inflammation can contribute to gingivitis and, in susceptible individuals, periodontitis.
2. Does heavy tartar automatically mean I have bone loss?
No. Heavy tartar increases concern about periodontal disease, but it does not prove that bone has been lost. Bone loss must be evaluated clinically and, when indicated, radiographically.
3. Can a dentist tell if I have periodontitis just by looking at my teeth?
Not reliably. A visual examination can identify warning signs, but periodontal probing, evaluation of attachment and other clinical findings are needed. Dental X-rays may be appropriate to assess supporting bone.
4. Can brushing remove hardened tartar?
No. Brushing and interdental cleaning are excellent for removing plaque and helping prevent additional calculus, but hardened tartar requires professional removal.
5. Can flossing remove existing tartar?
Floss can remove plaque and food debris between teeth, but it does not remove established hardened calculus. Professional treatment is required for calculus removal.
6. Will my gums stop bleeding immediately after cleaning?
Not necessarily. Inflamed gums may remain tender or bleed temporarily after treatment. As plaque control improves and inflammation decreases, bleeding should generally improve. Persistent bleeding should be discussed with your dentist.
7. Can gum disease cause loose lower front teeth?
Advanced periodontitis can damage the supporting tissues and bone around teeth, which can contribute to tooth mobility. A loose tooth should therefore receive a professional periodontal evaluation rather than being assumed to be caused by tartar alone.
8. If my gums look better after 14 days, am I cured?
Not necessarily. Improvement in redness, swelling and bleeding is encouraging, but it does not prove that periodontal disease has been eliminated. If attachment or bone loss was present, ongoing periodontal maintenance may be necessary.
9. Can lost jawbone grow back after tartar removal?
Routine scaling does not automatically regenerate bone that has already been lost. Periodontal treatment can control disease and, in selected cases, additional regenerative or surgical procedures may be considered by a periodontal specialist.
10. Do crowded lower front teeth increase tartar risk?
Crowding can create areas that are more difficult to clean. This can encourage plaque retention and make calculus buildup more likely. However, crowding alone does not establish a diagnosis of gum disease.
11. Do I need antibiotics for severe tartar?
Not automatically. Tartar is treated primarily by professional mechanical removal and appropriate periodontal care. Antibiotics are not a substitute for removing calculus and controlling the underlying periodontal problem. The decision to prescribe medication depends on the patient's specific diagnosis and clinical circumstances.
12. How often should I have my teeth professionally cleaned?
There is no single interval that is correct for everyone. Patients with healthy gums may have a different maintenance schedule from patients with periodontal disease. Your dentist should determine the interval based on your periodontal findings, oral hygiene and individual risk factors.
13. Can periodontal disease be prevented?
Much of periodontal disease risk can be reduced through effective daily plaque control, professional dental care, smoking cessation when applicable, and management of relevant health conditions. Gingivitis is generally preventable and reversible, while periodontitis requires professional management to control progression.
14. What is the most important thing to do if I have very heavy tartar?
Arrange a professional dental examination and cleaning rather than trying to remove it yourself.
The dentist should determine whether the problem is limited to calculus and gingivitis or whether periodontal pockets, attachment loss or bone loss are present.
15. What should I ask my dentist at the appointment?
A useful question is:
"Do I have gingivitis or periodontitis? What are my periodontal pocket measurements, is there any gum recession or tooth mobility, and do my X-rays show bone loss?"
Those answers provide much more useful information than judging the severity from the visible tartar alone.
Clinical Disclaimer
This educational content is based on the referenced clinical case and established periodontal-health guidance. A photograph or online article cannot replace an in-person dental examination. Diagnosis and treatment should be based on the patient's clinical examination, periodontal measurements and appropriate imaging when indicated.
The goal is not simply to make the teeth look cleaner. The goal is to determine whether the supporting gums and bone are healthy, control periodontal inflammation, preserve the natural teeth and establish a long-term maintenance plan.
Cebu dental clinic
For this case, I would specifically look for a dentist who can perform periodontal evaluation + professional scaling, rather than choosing a clinic solely because it advertises implants.
Your directory can be used here:
CebuDentalImplants.com Dental Clinic Map
Because you haven't provided your exact barangay/location, I can't honestly call one clinic the "nearest." If you're in the Mabolo/Cebu City area, current nearby options include:
- Near Dental Clinic - Mabolo
- Prestige Dental Clinic - Mabolo
- Joon Dental Family Care
- Affinity Dental Clinics Cebu
- One Nadela Dental Group - Cebu
What to tell the dentist
You can simply say:
"I have heavy calculus on the lower anterior teeth. Please check my periodontal pocket depths, gum recession, tooth mobility and whether I have bone loss before deciding whether I need regular scaling or scaling and root planing."
That will focus the appointment on the real clinical question: gingivitis versus periodontitis.
If there is facial swelling, fever, pus, rapidly increasing pain/swelling, difficulty swallowing, or difficulty breathing, don't wait for a 14-day healing period—seek urgent dental/medical evaluation.
Mabolo•Use precise location
Related Clinical Cases
Patients with lower front gum inflammation may also experience tartar buildup, periodontal disease, gum abscesses, or tooth decay. Explore these related clinical case studies.