Missing Teeth? Find Your Smile Again.

Back Molar with Deep Fissures Case Analysis
Image:
Severity:
Teeth Problems:
Dental Case Analysis: Back Molar with Deep Grooves and Early Decay Risk
Case Overview
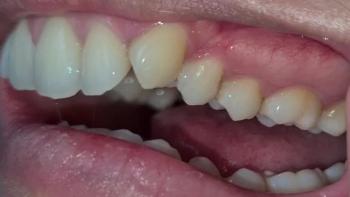
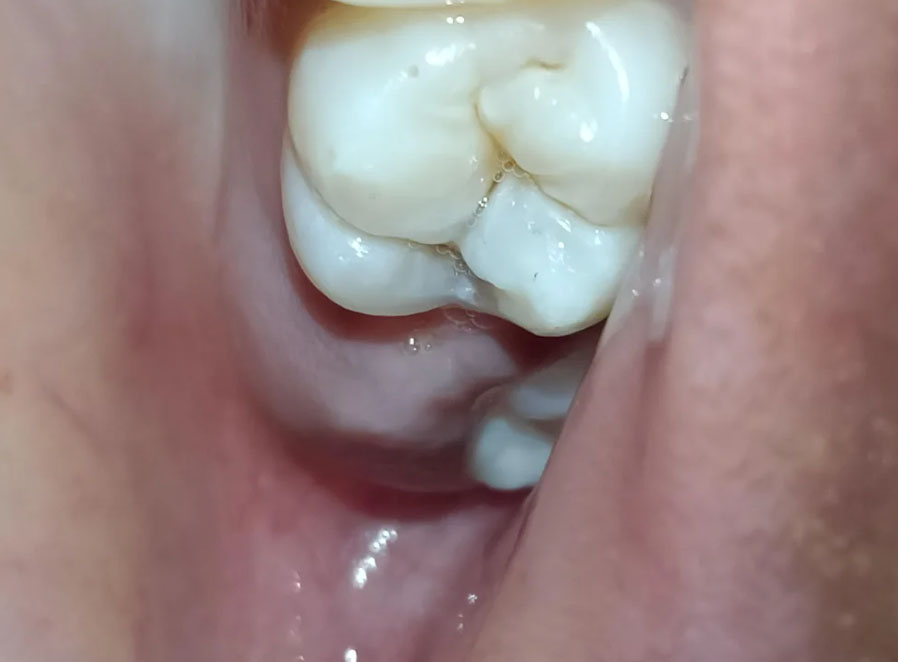
The image shows a posterior molar tooth with deep occlusal grooves (fissures). While the enamel surface appears mostly intact, the depth of the grooves creates a high risk area for early tooth decay due to plaque and food retention.
Zoom 100% Visual Examination
Observed Findings
-
Back molar with pronounced pits and fissures
-
Enamel surface appears smooth but irregular
-
Possible early staining within fissures
-
No obvious fracture or large cavity
-
Saliva pooling around grooves, indicating retention zones
-
Surrounding soft tissue appears normal
-
Adjacent teeth appear intact
Diagnosis
Primary Diagnosis
-
Deep occlusal fissures with high caries risk
Secondary Diagnosis
-
Possible early enamel demineralization
-
Increased susceptibility to future cavities
Treatment Objective
-
Prevent progression to dental caries
-
Seal or protect deep grooves
-
Maintain tooth structure and chewing function
Treatment Process to Execute
Step-by-Step Plan
-
Clinical examination and caries risk assessment
-
Dental X-ray if decay is suspected beneath enamel
-
Professional cleaning of fissures
-
Preventive treatment options:
-
Fissure sealant application
-
Preventive composite restoration if needed
-
-
Oral hygiene instruction and monitoring
Deep Fissures in Back Molars: Early Tooth Decay Risks, Prevention, and Treatment Options
Understanding the Clinical Significance of Deep Molar Grooves
Additional Dental Case Analysis
The chewing surfaces of molars contain natural anatomical grooves known as pits and fissures. These structures help the teeth grind food efficiently, but when the grooves are particularly narrow or deep, they can become areas where dental plaque and food debris accumulate.
In this back molar case, the visible surface shows pronounced occlusal fissures, with possible staining in the grooves and no obvious large cavity or fracture in the available image. These observations raise concern about an increased risk of pit-and-fissure dental caries, but they do not independently confirm active tooth decay.
From a molar-focused clinical perspective, the most important question is whether the fissures are simply deep anatomical features or whether the enamel has already begun to lose minerals or develop a cavity.
Early assessment is valuable because preventive treatment may preserve the natural tooth structure and reduce the likelihood of more extensive restorative procedures later.
1. Why Deep Fissures Increase the Risk of Molar Tooth Decay
Deep fissures create narrow spaces that can retain plaque and food debris. Because toothbrush bristles may not adequately clean the deepest parts of these grooves, bacteria can remain in the area even when the surrounding enamel looks relatively clean.
When oral bacteria metabolize fermentable carbohydrates, they produce acids that remove minerals from the enamel. Repeated acid attacks can gradually weaken the tooth surface and lead to a carious lesion.
Several factors influence whether decay develops:
-
Fissure anatomy: Deep, narrow grooves can be difficult to clean effectively.
-
Frequent sugar exposure: Repeated consumption of sugary snacks and drinks increases the frequency of acid attacks.
-
Plaque accumulation: Persistent bacterial biofilm increases the risk of demineralization.
-
Fluoride exposure: Fluoride helps strengthen enamel and supports remineralization of early mineral loss.
-
Saliva: Reduced salivary flow can make it harder for the mouth to neutralize acids and protect the teeth.
-
Previous dental caries: A history of cavities can indicate a higher ongoing risk of developing new lesions.
Deep fissures are a risk factor, not proof that a cavity already exists. Some molars have naturally deep grooves and remain healthy for years with appropriate preventive care.
2. What Can Be Observed in This Back Molar Case?
The available case image suggests several features that deserve clinical attention.
Pronounced occlusal grooves: The chewing surface contains deep pits and fissures that may retain plaque and food debris.
Possible fissure staining: Dark or discolored lines can result from external staining, accumulated debris, or changes associated with caries. Color alone cannot reliably distinguish harmless staining from active decay.
No obvious large cavity in the image: The visible surface does not show a clearly established large cavity. However, early decay or disease extending beneath the surface may not be apparent from a photograph.
No obvious fracture: A visible crack or major fracture is not clearly demonstrated in the available image. Fine cracks and symptoms arising from the tooth's internal structures cannot be ruled out through visual inspection alone.
Clinical interpretation
The appropriate provisional assessment is deep molar fissures with potential increased caries risk and possible early enamel changes.
A definitive diagnosis requires a dental examination. The dentist may clean and dry the tooth, inspect the fissures, assess the patient's caries risk, and obtain dental radiographs when indicated. Imaging is particularly useful when decay between teeth or beneath an apparently intact surface is suspected, although very early fissure lesions may not be visible on X-rays.
3. How Dentists Determine Whether a Deep Fissure Needs Treatment
The treatment decision depends on the condition of the enamel, whether a cavity has formed, and the patient's overall risk of developing caries.
Healthy enamel with deep grooves
If the tooth is intact and the grooves are difficult to clean, a dentist may recommend a preventive pit-and-fissure sealant. This protective material covers the susceptible grooves and helps prevent plaque and food from accumulating in them.
Sealants are especially well supported for preventing decay in children's and adolescents' molars, including newly erupted permanent molars. Selected adults may also benefit, depending on their tooth anatomy and caries risk.
Early enamel demineralization without a cavity
If mineral loss has occurred but the tooth surface remains intact, treatment may include fluoride toothpaste, professionally applied fluoride when appropriate, dietary changes, improved plaque control, and monitoring.
A sealant may also be appropriate for selected noncavitated fissure lesions. The dentist must first determine that the lesion can be adequately managed with this approach.
Established cavity
When tooth decay has created a physical cavity, a sealant alone may not be sufficient. Depending on the extent and activity of the lesion, the dentist may recommend a minimally invasive restoration or a conventional filling.
The objective is to control the disease while preserving as much healthy tooth structure as possible.
Extensive decay or structural damage
If the cavity is large or the remaining tooth is weakened, a larger restoration or crown may be required. If decay reaches the pulp, the tissue containing the tooth's nerves and blood vessels, root canal treatment or extraction may become necessary depending on the tooth's restorability and overall condition.
Deep fissures alone are not an indication for root canal treatment or extraction.
4. Why Preventive Dental Sealants Can Be Valuable
A dental sealant is a thin protective coating applied to the chewing surface of a tooth. It flows into susceptible pits and fissures and hardens to create a barrier.
The procedure commonly involves cleaning the surface, preparing the enamel according to the material's instructions, applying the sealant, allowing it to harden, and checking its coverage and bite.
Sealants can reduce the risk of fissure caries and may help arrest selected early, noncavitated lesions. They do not replace brushing, fluoride exposure, dietary management, or regular dental examinations.
Sealants can also wear down or become partially detached over time. The dentist should check their integrity during follow-up appointments and repair or replace them when needed.
5. Daily Care for Molars With Deep Fissures
Patients can reduce their risk of developing cavities by adopting consistent preventive habits.
-
Brush twice daily for approximately two minutes using fluoride toothpaste appropriate for their age.
-
Clean the chewing surfaces of the back teeth carefully, using a toothbrush with a head small enough to reach the molars.
-
Clean between teeth daily with floss or another suitable interdental cleaner.
-
Reduce the frequency of sugary snacks and drinks rather than focusing only on the total amount consumed.
-
Drink water regularly, particularly instead of frequently sipping sugary beverages.
-
Attend dental examinations at intervals recommended for the individual's caries risk.
For young children, parents or caregivers should help with brushing until the child can reliably clean all tooth surfaces.
Patients should not attempt to scrape, drill, or cut deep fissures at home. Such actions can injure the enamel or gums.
6. Warning Signs That Require Dental Assessment
Deep fissures may not cause symptoms during the early stages of decay. The absence of pain therefore does not guarantee that the tooth is healthy.
Arrange a dental assessment if any of the following develops:
-
New sensitivity to cold, heat, or sweet foods.
-
Pain when biting or chewing.
-
Food repeatedly becoming trapped in the same groove.
-
A visible hole, rough area, or change in the tooth's surface.
-
Persistent toothache or pain that occurs without an obvious trigger.
Seek urgent dental care if pain becomes severe or swelling develops. Facial or neck swelling, fever with worsening dental symptoms, difficulty swallowing, or difficulty breathing may indicate a spreading infection. Difficulty breathing or swallowing requires emergency medical attention.
7. Expert Case Conclusion
This case highlights the importance of evaluating deep occlusal fissures before substantial tooth damage develops. The visible anatomy suggests an area that may be susceptible to plaque retention and fissure caries, but the available image cannot establish whether active decay is present.
A clinically appropriate approach is to assess the cleaned and dried molar, determine the patient's caries risk, and select treatment according to the actual condition of the enamel.
If the fissures are healthy, preventive sealing may be appropriate. If early mineral loss is present without surface breakdown, nonrestorative management or sealing may be considered. If a cavity has formed, restorative treatment may be necessary.
The central clinical principle is to prevent decay when possible, detect it early, and preserve healthy molar structure whenever treatment is required.
Medical note: This article provides general educational information and is not a substitute for an examination by a licensed dentist. A photograph alone cannot confirm the presence, depth, or activity of dental caries.
Deep Grooves in Back Molars: Early Tooth Decay Risk, Dental Sealants, and Treatment Options
Why Deep Fissures in Back Molars Need Dental Attention
The chewing surfaces of molars naturally contain small pits and grooves called pits and fissures. These anatomical features help the teeth grind food effectively, but deep or narrow grooves can also create areas where plaque and food debris accumulate.
When plaque bacteria break down sugars and fermentable carbohydrates, they produce acids that remove minerals from the tooth enamel. Repeated acid attacks can weaken the enamel and eventually lead to tooth decay. Deep fissures may increase the risk of decay because they can be difficult to clean thoroughly with ordinary brushing.
According to the National Institute of Dental and Craniofacial Research (NIDCR), early tooth decay may develop without noticeable symptoms. A tooth can therefore have an early carious lesion even when the patient does not experience pain. Source: NIDCR — Tooth Decay
Clinical Case Discussion: Back Molar With Deep Fissures
In the referenced case, the back molar is described as having pronounced grooves on its chewing surface, with possible early staining and no obvious large cavity or fracture in the available image.
These findings raise concern about potential plaque retention and early caries. However, deep grooves and dark staining do not automatically mean that a tooth has active decay.
Findings that require careful assessment
-
Deep occlusal fissures: Narrow grooves may retain plaque and food particles, making cleaning more difficult.
-
Staining within the grooves: Brown or dark discoloration may represent harmless staining, arrested decay, or active caries. Color alone cannot establish the diagnosis.
-
Possible early enamel demineralization: The dentist should assess whether the enamel is losing minerals or whether a cavity has already formed.
-
No obvious large cavity: The absence of a visible hole does not exclude early decay or disease extending beneath the enamel.
-
Surrounding gum tissues: The gums should be assessed for redness, swelling, bleeding, and food impaction.
Clinical interpretation: The main concern is the possibility of early occlusal caries in a molar with deep fissures. A definitive diagnosis requires a clinical examination, and dental radiographs may be indicated depending on the findings and suspected extent of disease.
What Happens If Deep Molar Fissures Are Left Untreated?
Deep fissures do not inevitably develop into cavities. However, when active decay develops and the underlying causes remain uncontrolled, the condition can progress through several stages.
Stage 1: Deep fissures without detectable decay
The enamel remains intact, but the grooves may retain plaque. Preventive care, fluoride toothpaste, professional monitoring, and a dental sealant when appropriate can help reduce the risk of decay.
Stage 2: Early enamel demineralization
Repeated acid exposure removes minerals from the enamel. The affected area may develop a chalky white appearance or other discoloration, although early lesions are not always visible to the patient.
At this stage, a dentist may recommend fluoride treatment, dietary changes, plaque control, and monitoring. Selected noncavitated lesions may also be managed with sealants or other minimally invasive treatments.
Stage 3: A cavity develops
If mineral loss continues, the enamel can break down and form a cavity. Once a cavity has formed, fluoride alone generally cannot rebuild the missing tooth structure. The dentist may need to remove damaged tissue and restore the tooth with a filling.
Stage 4: Decay reaches the dentin
Dentin lies beneath the enamel and is less mineralized. As decay advances into dentin, the tooth may become sensitive to sweets, cold, heat, or pressure. Some cavities remain painless despite significant damage.
Treatment depends on the depth and extent of the lesion and may require a larger restoration.
Stage 5: Pulp inflammation or infection
Advanced decay can irritate or infect the dental pulp, which contains nerves and blood vessels. Possible symptoms include spontaneous toothache, lingering sensitivity to temperature, pain that interrupts sleep, or tenderness when biting.
Depending on the pulp diagnosis and whether the tooth can be restored, treatment may involve vital pulp therapy in selected cases, root canal treatment, or extraction if the tooth cannot be predictably saved.
Untreated infection can sometimes progress to an abscess and spread into nearby tissues.
Important: These stages describe a possible progression, not a prediction that every deep fissure will develop into advanced disease.
Treatment Options for Deep Grooves in Molars
The correct treatment depends on whether the tooth is healthy, has early noncavitated decay, contains a cavity, or has deeper structural damage.
1. Dental sealants
A dental sealant is a thin protective material applied to the chewing surface of a tooth. It flows into pits and fissures and creates a barrier that helps prevent plaque and food debris from accumulating in those areas.
Sealants are particularly useful for children and adolescents with newly erupted permanent molars, although selected adults may also benefit based on their cavity risk and the condition of the tooth.
A sealant may also help manage selected noncavitated occlusal caries lesions when the tooth can be adequately assessed and sealed. It is not a substitute for appropriate treatment of a cavity that requires restoration.
2. Fluoride treatment
Fluoride supports enamel remineralization and helps reduce the risk of further mineral loss. A dentist may recommend professional fluoride varnish or other fluoride products according to the patient's age, caries risk, and clinical findings.
Fluoride can help manage early noncavitated lesions, but it cannot replace tooth structure already lost through cavitation.
3. Tooth-colored filling
When decay has produced a cavity, the dentist may remove the affected tooth tissue and restore the defect with a suitable filling material, such as composite resin.
The amount of tooth preparation depends on the lesion's extent and the need to preserve healthy tooth structure.
4. Larger restoration or dental crown
A larger cavity or a molar weakened by substantial structural damage may require a more extensive restoration. A crown may be appropriate when sufficient tooth structure has been lost that a conventional filling would not provide adequate long-term protection.
A crown is not automatically necessary simply because the molar has deep fissures.
5. Root canal treatment
If decay causes irreversible pulp inflammation or pulp necrosis, root canal treatment may be indicated when the tooth is restorable. The procedure involves treating the pulp space and sealing the root canals, followed by an appropriate restoration.
Root canal treatment is not needed for every cavity or every sensitive tooth.
Clinical principle: Choose the least invasive treatment that can predictably control the disease and preserve the tooth, while avoiding unnecessary drilling or restoration.
References: American Dental Association — Dental Sealants and NIDCR — Dental Fillings.
How Dentists Diagnose Decay in Deep Fissures
A dental examination may include:
-
Visual examination: The dentist inspects the grooves for discoloration, enamel breakdown, visible cavities, and other abnormalities.
-
Cleaning and drying: Removing plaque and examining a clean, dry surface can help reveal early changes in the enamel.
-
Clinical assessment: The dentist evaluates the lesion's appearance and activity, the patient's caries risk, symptoms, and previous dental history. Gentle examination may be appropriate; forceful probing that damages an early lesion should be avoided.
-
Dental X-rays when indicated: Bitewing or other appropriate radiographs may help identify decay extending into dentin or areas that cannot be assessed visually. X-rays do not detect every early occlusal lesion.
-
Pulp and structural assessment: If symptoms suggest deeper disease, additional tests may assess pulp status, tenderness, bite-related pain, or possible cracks.
No single visual sign or diagnostic test should be interpreted in isolation.
How to Prevent Tooth Decay in Back Molars
Patients with deep molar grooves can lower their risk of cavities through consistent preventive care.
-
Brush twice daily with fluoride toothpaste, paying particular attention to the chewing surfaces of the back teeth.
-
Clean between the teeth daily using floss or an appropriate interdental cleaner.
-
Reduce frequent consumption of sugary foods and drinks, particularly repeated sipping or snacking throughout the day.
-
Drink water regularly and maintain a balanced diet.
-
Ask a dentist whether fissure sealants or professional fluoride treatment are appropriate.
-
Attend regular dental examinations based on individual risk.
-
Seek assessment for new sensitivity, persistent food trapping, pain when biting, or visible changes in a molar.
Good oral hygiene is important, but deep grooves can remain difficult to clean. Professional prevention and individualized monitoring may therefore be beneficial.
When Should You See a Dentist Urgently?
Arrange a dental appointment promptly if a back molar develops persistent sensitivity, spontaneous pain, a visible cavity, a chipped area, or pain when chewing.
Seek urgent dental care for facial or gum swelling, pus, fever associated with a suspected dental infection, or rapidly worsening pain.
Go to an emergency department immediately if swelling causes difficulty breathing or swallowing, or spreads rapidly into the neck or floor of the mouth. These may indicate a serious spreading infection.
Do not attempt to treat a suspected dental abscess with leftover antibiotics or by placing medication directly into the tooth. Dental infections generally require treatment of the source, and antibiotics are indicated only in selected circumstances.
Expert Dental Conclusion
Deep fissures in back molars are common anatomical features, but their depth and shape can increase the risk of plaque retention and occlusal caries. Early assessment is valuable because a noncavitated lesion may be managed conservatively, whereas an established cavity may require restorative treatment.
For the referenced case, the appropriate next step is to confirm whether the grooves are sound, stained, affected by early demineralization, or associated with a cavity. The dentist can then recommend preventive treatment, a sealant, a filling, or more extensive care according to the actual findings.
The goal is to detect disease early, preserve healthy tooth structure, and prevent avoidable pain and complications.
Healing and Treatment Time Frame
First 14 Days
-
No significant discomfort expected
-
Sealant or restoration stabilizes the surface
-
Normal chewing resumes immediately
After 14 Days
-
Tooth remains protected from decay
-
Low risk of cavity development if hygiene is maintained
If Treatment Is Delayed
Issues That May Scale Up
-
Bacteria penetration into deep grooves
-
Development of occlusal cavity
-
Need for drilling and filling
-
Possible progression to deeper dentin decay
Professional Comments
-
Condition is preventive and manageable
-
Early action avoids invasive treatment
-
Deep fissures are common cavity initiation points
Recommendation
Visit a dental clinic for preventive care and evaluation.
Find a clinic near you:
https://cebudentalimplants.com/map-dental-clinic
Video :
Related Clinical Cases
Patients with lower front gum inflammation may also experience tartar buildup, periodontal disease, gum abscesses, or tooth decay. Explore these related clinical case studies.