Your Smile, Perfected with Precision.

Recurrent Jawbone Infection With Facial Rash - Dental Case Analysis
Image:
Severity:
Recurrent Jawbone Infection and Persistent Facial Rash — Warning Signs, Complications, and Treatment
Why Can a Dental Infection Cause a Recurring Facial Rash?
A persistent or recurring rash, small lump, or open sore along the cheek, chin, or jawline may occasionally originate from an infection inside a tooth rather than from a primary skin disorder. One possible explanation is an odontogenic cutaneous sinus tract, a channel through which infected material drains from a diseased tooth or surrounding tissues toward the skin.
This can occur when bacteria enter the dental pulp through deep tooth decay, a crack, trauma, or a failed previous dental treatment. Infection may extend beyond the root tip into surrounding tissues and, in some cases, through the jawbone and soft tissues until it reaches the skin surface.
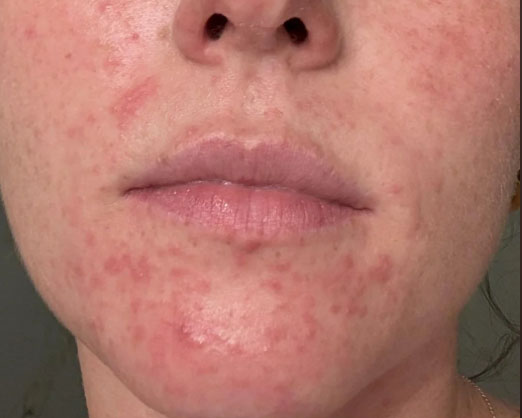
The resulting lesion may appear as a red bump, crusted sore, intermittently draining opening, or area of skin discoloration. Some patients experience little toothache or no obvious dental pain, even when significant disease is present.
However, a facial rash alone does not confirm a dental infection or osteomyelitis. Dermatologic conditions, cysts, other infections, and occasionally more serious lesions must also be considered. A proper dental and medical examination is necessary to establish the cause.
What Does Recurrent Jawbone Infection Mean?
Recurrent jawbone infection means that symptoms or evidence of infection have returned after an earlier episode of treatment. Possible explanations include:
-
Persistent infection around a tooth root: Bacteria remain in an infected root canal or surrounding tissues.
-
Incomplete root canal treatment: Complex, narrow, or calcified canals may make it difficult to clean and seal every infected area.
-
Persistent apical inflammation: Infection or inflammation remains around the root tip and may continue to damage nearby bone.
-
Chronic osteomyelitis: In some cases, infection and inflammation involve the jawbone itself.
-
Infection around a dental implant: Peri-implant infection can damage supporting tissues and bone, although a facial rash does not establish this diagnosis.
-
A separate or previously undetected condition: A skin lesion may have another cause and require additional investigation.
A recurring facial lesion should therefore prompt a reassessment of the original diagnosis, the tooth involved, the quality of previous treatment, and whether the infection has extended into bone.
How Dentists Investigate a Possible Jawbone Infection
An endodontist or oral and maxillofacial surgeon may coordinate the evaluation, depending on the findings.
1. Clinical and dental examination
The dentist examines the affected facial area, nearby teeth, gums, previous restorations, root canal treatment, and any dental implants. The history should include when the lesion first appeared, whether it drains, and whether it improves and then returns.
2. Pulp testing and dental X-rays
Pulp sensibility tests help assess whether a tooth may have a diseased or non-vital pulp. Periapical radiographs can reveal changes around tooth roots, although early disease may not be clearly visible.
3. Advanced imaging when indicated
Cone-beam computed tomography (CBCT) may help identify the extent of a root-related lesion, bone changes, or cortical bone perforation when conventional X-rays do not provide enough information. CT or MRI may be needed if a more extensive bone or soft-tissue infection is suspected.
4. Specialist assessment and additional tests
If the diagnosis remains uncertain, clinicians may consider microbiological sampling, blood tests, or tissue biopsy depending on the clinical situation. A persistent lesion that fails to resolve after appropriate dental treatment should be reassessed rather than automatically assumed to be dental in origin.
Treatment Options for Recurrent Infection
Treatment depends on the source, severity, restorability of the affected tooth, and whether the jawbone is involved.
-
Root canal treatment or retreatment: May preserve a restorable tooth when infection originates inside its root canal system.
-
Endodontic surgery: May be appropriate when persistent disease around the root tip cannot be adequately managed through conventional treatment.
-
Extraction: May be necessary if a tooth is not predictably restorable or its infection cannot be controlled with tooth-preserving treatment.
-
Treatment of confirmed osteomyelitis: May require specialist-directed antibiotics, drainage or surgical removal of infected or nonviable tissue, and follow-up imaging or examinations.
-
Treatment of implant-related disease: Requires assessment of the implant, surrounding tissues, bone loss, and the feasibility of controlling the infection.
Antibiotics are not a substitute for eliminating the underlying dental source. A clinician may prescribe them when there is spreading infection, systemic involvement, or another appropriate indication. Not every localized dental infection requires antibiotics, and patients should not self-prescribe leftover medication.
The facial lesion may improve after the source of infection is treated, but complete healing and bone recovery can take longer. Persistent drainage, a non-healing wound, or continuing bone changes require follow-up.
What Could Happen If the Condition Is Neglected?
Leaving a genuine dental infection untreated can allow the disease to persist or progress. The following scenarios describe possible complications, not inevitable outcomes.
Scenario 1: The facial rash repeatedly returns
A small sore near the jaw improves temporarily, then reappears. The patient applies creams or receives repeated courses of antibiotics without investigating the tooth. If the lesion is a dental sinus tract, the source remains and drainage may continue until the underlying infection is treated.
Scenario 2: Progressive damage around the tooth root
Persistent infection around the root tip may lead to further loss of supporting bone. The tooth may become more difficult to preserve, potentially requiring more complex treatment or extraction.
Scenario 3: Infection extends into the jawbone
In selected cases, infection can involve the bone itself and develop into osteomyelitis. Patients may experience persistent pain, swelling, drainage, or changes in bone structure. Some cases require prolonged specialist treatment and surgery.
Scenario 4: An abscess spreads into facial or neck spaces
A spreading odontogenic infection can cause increasing swelling, pain, difficulty opening the mouth, or systemic illness. Severe infection can threaten the airway or spread to deeper tissues. These complications are uncommon but potentially life-threatening.
Scenario 5: A different skin or bone disorder is overlooked
Assuming that every recurring facial lesion comes from a tooth can delay diagnosis of another condition. If the lesion persists despite appropriate treatment, the dentist and medical team should reconsider the differential diagnosis and arrange further investigation.
When Should You Seek Urgent Care?
Arrange a prompt dental appointment for a recurring facial sore, drainage, swelling, or suspected tooth-root infection, even if the tooth does not hurt.
Seek emergency medical care immediately if you develop:
-
Difficulty breathing or swallowing.
-
Rapidly increasing swelling of the face, jaw, floor of the mouth, or neck.
-
Swelling around the eye accompanied by eye pain, impaired vision, or difficulty moving the eye.
-
Severe illness, confusion, or rapidly worsening symptoms.
Fever, spreading redness, increasing pain, or difficulty opening the mouth also warrant urgent same-day assessment. People with weakened immunity may need a lower threshold for urgent evaluation.
Expert Dental Perspective
The most important clinical principle is to identify the source rather than repeatedly treat the visible skin lesion alone. When a facial lesion repeatedly drains or returns near the jaw, a dental origin should be considered alongside dermatologic and other medical causes.
Early diagnosis can help preserve a treatable tooth, prevent avoidable procedures, and reduce the risk of complications. The correct treatment should be based on examination and appropriate imaging—not on the appearance of the rash alone.
Medical disclaimer: This educational content cannot diagnose an individual patient. A qualified dentist, endodontist, oral surgeon, or medical clinician must determine whether the lesion represents a dental sinus tract, jawbone infection, skin disease, or another condition.
Dental Case Analysis – Recurrent Jawbone Infection With Persistent Facial Rash
Case Overview
This case involves a patient with a history of bacterial infection in the lower jawbone affecting teeth 25 and 26, complicated by bone loss and incomplete root canal treatment due to canal calcification. Years later, imaging shows recurrent infection, alongside a persistent facial rash localized to the same area, causing emotional and physical distress.
Client History Summary
Dental History
-
Initial bacterial infection at roots of teeth 25 and 26 (5 years ago)
-
Bone loss caused by infection
-
Root canal treatment performed on both teeth
-
One tooth incompletely treated due to calcified canal
-
Six-month follow-up showed no active symptoms
-
Recent 3D scans show bacteria has returned with minor bone loss
-
Endodontist recommendation: apicoectomy
Current Symptoms
-
Persistent facial rash localized to lower face and chin
-
Redness, dryness, irritation
-
Rash described as chronic and emotionally overwhelming
-
Skin care limited to gentle cleanser, Aquaphor, and beef tallow
Deep Clinical Examination
Dental Findings
-
Chronic apical infection likely originating from the partially treated root canal
-
Calcified canal may harbor residual bacteria
-
Ongoing low-grade infection consistent with bone loss on imaging
-
Infection appears chronic rather than acute, explaining minimal dental pain
Facial Skin Findings
-
Rash distribution corresponds anatomically with infected jaw area
-
Appearance suggests chronic inflammatory response
-
Possible immune or inflammatory reaction triggered by long-term infection
-
Not uncommon for chronic dental infections to present extra-oral symptoms
Diagnosis
Primary Dental Diagnosis
-
Recurrent chronic apical periodontitis
-
Persistent periapical bacterial infection
-
Incomplete endodontic seal due to canal calcification
Secondary Consideration
-
Chronic inflammation possibly contributing to facial skin reaction
-
Dental infection acting as a long-term inflammatory stressor
Direct causation cannot be confirmed, but correlation is clinically plausible.
Time Frame to Heal
After Apicoectomy
-
Initial wound healing: 7–14 days
-
Swelling and inflammation reduction: 1–2 weeks
-
Bone healing begins: 4–8 weeks
-
Radiographic bone improvement: 3–6 months
Facial Rash Outlook
-
If infection contributes to inflammation, improvement may occur weeks to months after dental source removal
-
Persistent rash may still require dermatologic care
Process to Execute (14-Day Focus)
Days 1–3
-
Surgical consultation and CBCT review
-
Confirm apicoectomy necessity
-
Pre-operative infection management
Days 4–7
-
Apicoectomy procedure
-
Removal of infected root tip
-
Curettage of infected bone tissue
-
Retrograde root sealing
Days 8–14
-
Post-operative follow-up
-
Monitor pain, swelling, and healing
-
Observe changes in facial rash
-
Adjust care plan if symptoms persist
Issues That Will Scale Up If Untreated
-
Progressive jawbone loss
-
Chronic infection spread
-
Possible abscess formation
-
Increased surgical complexity
-
Tooth loss
-
Persistent systemic inflammation
-
Long-term skin conditions
Clinical Comments
Chronic dental infections can quietly affect the body beyond the mouth. Many patients report feeling isolated or unheard, especially when symptoms are visible and persistent. Addressing the infection source often brings both physical relief and emotional reassurance.
A team approach involving an oral surgeon and dermatologist is strongly recommended.
Find a Dental Clinic Near You
Search for a qualified dental clinic in your area:
https://cebudentalimplants.com/map-dental-clinic
Related Clinical Cases
Patients with lower front gum inflammation may also experience tartar buildup, periodontal disease, gum abscesses, or tooth decay. Explore these related clinical case studies.