Modern Dentistry, Timeless Smiles.

Is This Gum Recession? Braces, Gum Inflammation & What Happens in 14 Days
Image:
Severity:
Teeth Problems:
Gum Recession and Gum Inflammation During Braces Treatment
Why Do Gums Become Inflamed During Orthodontic Treatment?
From an orthodontic perspective, swollen or bleeding gums during braces treatment should be evaluated rather than dismissed as an unavoidable side effect. Brackets, wires, and other orthodontic appliances create additional areas where dental plaque can accumulate, making effective brushing and interdental cleaning more challenging.
When plaque remains along the gumline, the gum tissue may become red, swollen, tender, and prone to bleeding. This condition is commonly associated with plaque-induced gingivitis, an early form of gum disease. With appropriate plaque control and professional care, gingivitis can often be reversed before permanent damage occurs.
However, persistent inflammation may indicate inadequate plaque removal, an appliance-related irritation, or an underlying periodontal problem. A dental examination is necessary to identify the cause and determine whether additional treatment is required.
Can Gum Inflammation Develop Into Gum Recession Within 14 Days?
A two-week period can be useful for monitoring changes in gum inflammation, but it is not a reliable deadline for determining whether gum recession will develop or heal.
Gingivitis can become noticeable over a relatively short period when plaque accumulates around braces. Gum recession, by contrast, occurs when the gum margin moves away from its previous position, exposing more of the tooth or its root. Recession may be associated with pre-existing gum disease, thin gum tissue, tooth position, brushing trauma, or orthodontic tooth movement in susceptible patients.
If swollen gums become less puffy after inflammation improves, the teeth may appear longer or the roots may become more visible. This does not necessarily mean that new recession developed during those two weeks; some of the apparent change may reflect the resolution of swelling.
Clinical takeaway: Do not diagnose gum recession based on photographs alone or a fixed 14-day timeline. A dentist or periodontist can assess gum-margin position, periodontal pocket depths, tissue attachment, and, when indicated, supporting bone levels.
What Should Patients Do During the First 14 Days of Gum Inflammation?
Days 1–3: Improve plaque removal and assess irritation.
-
Brush gently with a soft-bristled toothbrush and fluoride toothpaste, paying particular attention to the gumline and the areas above and below each bracket.
-
Use an orthodontic or interdental brush to clean around brackets and beneath the archwire.
-
Clean between the teeth daily using an appropriate flossing aid or another interdental cleaning method recommended by your dental professional.
-
Check whether a loose bracket or protruding wire is rubbing against the gums.
Days 4–7: Monitor symptoms and arrange professional assessment if needed.
Continue consistent cleaning and observe whether redness, swelling, tenderness, and bleeding are improving. If symptoms persist, worsen, or occur frequently, contact your dentist or orthodontist. Do not wait until day 14 if the gums are significantly swollen, painful, or bleeding heavily.
Days 8–14: Reassess gum health rather than assuming recovery.
If inflammation is improving, continue the cleaning routine and attend scheduled dental appointments. If the gums remain swollen or bleed regularly, a professional examination may be needed to assess plaque and tartar accumulation, periodontal disease, or mechanical irritation.
Two weeks is a monitoring period, not a guaranteed healing window. Established periodontal damage or true gum recession may require a different treatment plan.
How Is Gum Inflammation Treated in Patients Wearing Braces?
Treatment depends on the underlying cause and severity.
-
Plaque-induced gingivitis: Improve brushing and interdental cleaning. Professional cleaning may be necessary if plaque has hardened into tartar.
-
Persistent periodontal inflammation: A dentist or periodontist may measure periodontal pockets and recommend additional periodontal treatment where indicated.
-
Appliance-related irritation: The orthodontist can assess a rubbing bracket, wire, or other appliance and make appropriate adjustments.
-
Gum recession: The clinician evaluates the amount of recession, sensitivity, tissue thickness, tooth position, and periodontal support. Selected cases may benefit from periodontal consultation or gum-grafting procedures.
Patients should not stop orthodontic treatment, change their own braces, or attempt to move teeth independently. If periodontal health is deteriorating, the orthodontist and periodontal clinician may need to coordinate care and reconsider the timing or mechanics of tooth movement.
When Is Gum Inflammation a Warning Sign?
Seek prompt dental assessment for persistent or worsening swelling, repeated bleeding, pus, increasing tenderness, gum tissue growing around brackets, or a newly noticeable area of exposed tooth root.
Facial swelling, fever, or rapidly worsening pain may indicate a more serious infection and warrants urgent assessment. Difficulty breathing or swallowing, or swelling that threatens the airway, requires emergency medical care.
Expert Clinical Perspective
The goal of orthodontic treatment is not simply to align the teeth. The gums, periodontal ligament, and supporting bone must also remain healthy throughout treatment. Good plaque control is essential, but it cannot correct every cause of gum inflammation or recession.
Patients with existing periodontal disease, a history of gum recession, or thin gum tissue may require individualized monitoring before and during orthodontic treatment. Early assessment helps the dental team distinguish reversible inflammation from changes in the supporting tissues that may need more specialized care.
Medical note: This educational information does not replace an examination by a licensed dentist or orthodontist. Individual diagnosis and treatment depend on clinical findings.
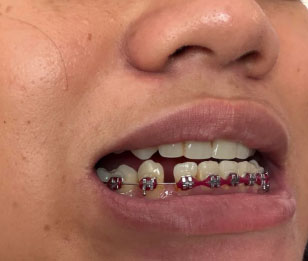
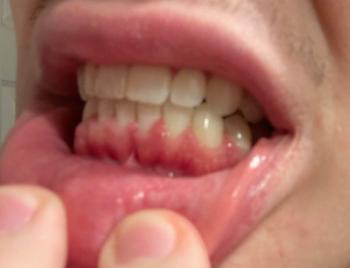
I examined the uploaded photo at 100% and enlarged the lower teeth/gum area. This is a visual assessment only—not a definitive dental diagnosis. A dentist/orthodontist needs periodontal probing and, if indicated, X-rays to determine whether there is true gum recession or bone loss. The American Association of Orthodontists specifically notes that gum health cannot be accurately evaluated from appearance alone.
1. What I can see in this case
Lower front teeth with fixed braces:
- Brackets and archwire are clearly visible.
- A red elastic power chain runs across several lower teeth.
- The lower anterior gum margin appears quite close to the brackets, with areas that look irritated/red.
- There appears to be localized gum inflammation, particularly around the bracket/gingival margins.
- The photograph does not provide enough evidence to confirm significant gingival recession.
- I cannot determine the amount of periodontal pocketing, attachment loss, or supporting bone loss from this photograph.
2. Is this gum regression/recession?
Possibly, but I would not diagnose recession from this photograph alone.
True gingival recession means the gum margin has moved toward the root, exposing more of the tooth/root surface. A tooth appearing longer can be a warning sign, but recession needs to be measured clinically.
In this particular image, inflammation around the braces may make the gumline look abnormal, so the first question should be:
Is there actual loss of gum attachment, or is this mainly gingival inflammation/irritation associated with orthodontic treatment?
That distinction is important.
3. Main issues I would investigate
Priority 1 — Gingival inflammation
- Redness/swelling around brackets
- Plaque accumulation around the orthodontic hardware
- Possible bleeding during brushing/flossing
- Difficulty cleaning underneath the archwire
Priority 2 — Possible localized recession
- Check whether any lower tooth has a visibly lower gum margin than neighboring teeth.
- Measure recession in millimeters.
- Check the thickness/width of attached gingiva.
- Determine whether the tooth has been moved too far toward the outer side of the supporting bone.
Priority 3 — Periodontal support
The clinician should check:
- Periodontal pocket depths
- Bleeding on probing
- Clinical attachment levels
- Tooth mobility
- Gum thickness
- Bone level on radiographs where appropriate
A comprehensive periodontal evaluation specifically examines the teeth, plaque, gums, bite, bone structure and risk factors.
4. Why braces matter here
Orthodontic tooth movement can affect the periodontal tissues. If periodontal health is poor before or during orthodontic movement, there can be increased risk of recession and other periodontal complications.
That does not mean the braces caused recession in this case. It means the gum condition should be evaluated before continuing aggressive tooth movement.
5. If the problem is mainly inflammation
The first treatment phase may involve:
- Orthodontic examination.
- Periodontal examination.
- Professional cleaning.
- Improved brushing around every bracket.
- Interdental cleaning/interdental brushes.
- Reassessment of gum swelling and bleeding.
- Orthodontic adjustment if excessive forces or tooth positioning are contributing.
- Periodontal treatment if deeper pockets or periodontal disease are found.
If periodontal disease is present, scaling and root planing may be considered; periodontal maintenance is often needed afterward.
6. What happens in 14 days?
14 days can be enough to see meaningful improvement in inflammation, but it is NOT a guaranteed healing period for gum recession.
A reasonable 14-day monitoring approach would be:
| Period | What to monitor |
|---|---|
| Days 1–3 | Bleeding, tenderness, swelling, plaque around brackets |
| Days 4–7 | Gum redness/swelling and cleaning effectiveness |
| Days 8–14 | Whether inflammation is clearly decreasing |
| After 14 days | Re-examination and comparison with baseline |
If the gum is simply inflamed from plaque/orthodontic irritation, improvement can occur relatively quickly after effective professional cleaning and better home care.
True recession is different. Lost gum tissue does not simply "grow back" in 14 days. If recession is confirmed, the clinician must determine its cause, severity and whether observation, orthodontic modification, periodontal treatment or soft-tissue surgery is appropriate.
7. What could "scale up" if ignored?
This is the part I would emphasize to the patient.
If inflammation continues during orthodontic treatment, the problem can potentially progress from:
Plaque accumulation → gingival inflammation → persistent periodontal inflammation → attachment/bone loss or recession → increased tooth sensitivity/esthetic changes → potentially more complicated periodontal treatment.
The American Academy of Periodontology lists receding gums, bleeding, swelling, loose teeth, pus and persistent bad breath among warning signs that warrant professional evaluation.
Also, moving teeth when periodontal health is inadequate can increase the risk of recession, root shortening and, in severe circumstances, tooth loss.
8. My assessment of this photograph
Visual concern level: Moderate — needs examination, but this photograph does not demonstrate an obvious severe periodontal emergency.
The most obvious visible issue is gingival irritation/inflammation around the lower orthodontic appliances.
Possible gum recession: YES — needs measurement.
Confirmed gum recession from photograph: NO.
Confirmed bone loss: NO — requires clinical examination/X-ray.
14-day healing: Possible improvement if inflammation is the main problem, but not a guarantee and not sufficient to reverse established recession.
9. What I would ask the dentist/orthodontist to check
Ask specifically:
"Can you measure the gum recession around each lower front tooth in millimeters and check the periodontal pocket depths and bone support before continuing orthodontic movement?"
That gives the patient a much more useful answer than simply asking whether the gum "looks recessed."
If there is significant recession or questionable bone support, a periodontist + orthodontist evaluation is appropriate. Periodontists specifically evaluate recession, periodontal pockets, tooth contact/bite, tooth mobility and underlying bone with appropriate imaging.
Find a nearby dental clinic
Your directory can be used to locate a clinic by area, and it currently lists locations across Cebu/Visayas and other regions.
Find the nearest dental clinic using your directory
Important: If the patient develops rapidly increasing swelling, pus, significant pain, fever, facial swelling, or a loose tooth, don't wait 14 days—seek a dental evaluation promptly.
Related Clinical Cases
Patients with lower front gum inflammation may also experience tartar buildup, periodontal disease, gum abscesses, or tooth decay. Explore these related clinical case studies.
Other topics:
Other Dental Clinic
 |
 |
 |
 |