Missing Teeth? Find Your Smile Again.

Dental X-Ray Case Analysis: Severe Tooth Crowding, Eruption Problems, and What Happens If Treatment Is Delayed 14 Days
Image:
Severity:
Teeth Problems:
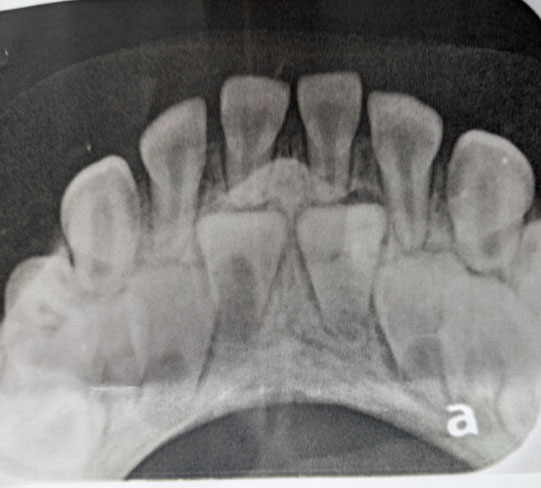
The image appears to be an anterior dental occlusal radiograph, likely showing a developing/mixed-dentition situation. However, an X-ray alone cannot provide a definitive diagnosis or replace an in-person examination.
1. What I can see
The most important finding is crowding/overlap of the anterior teeth with developing or unerupted teeth positioned behind/among the erupted teeth.
Approximate tooth-by-tooth assessment
| Area | X-ray appearance | Concern |
|---|---|---|
| Upper/lower anterior central region | Multiple overlapping tooth structures | Moderate–high concern for eruption/crowding problem |
| Central incisors | Roots/developing structures visible | Need assessment of eruption direction and root development |
| Lateral incisor regions | Crowding/overlap | Possible displacement/ectopic eruption |
| Canine regions | Developing tooth structures appear crowded | Need monitoring of eruption path |
| Bone around anterior teeth | No obvious large destructive radiolucency visible on this image | Reassuring, but this image is limited |
| Root areas | No obvious large apical lesion visible | Cannot exclude pathology without additional views |
| Gum/periodontal structures | Difficult to evaluate accurately from this projection | Clinical examination required |
I do not see a large obvious abscess, destructive bone lesion, or massive cyst on this particular image. That is reassuring.
The bigger issue appears to be tooth position, eruption and crowding, rather than an obvious acute infection.
2. Important limitation
This is a single 2-D radiograph. There is considerable superimposition, so I would not diagnose a specific impacted tooth, supernumerary tooth, cyst, or orthodontic condition with certainty from this image alone.
For a definitive evaluation, a dentist/orthodontist may need:
- Clinical examination
- Panoramic X-ray
- Periapical X-rays
- Possibly a cephalometric X-ray
- CBCT/3-D imaging only if clinically justified, particularly if an impacted tooth is close to another root or an important anatomical structure
A child's/adolescent's age is also very important because normal eruption timing changes the interpretation considerably.
3. If treatment is delayed for 14 days
This is where I would distinguish between orthodontic/eruption problems and infection.
If this is primarily an eruption/crowding problem
A 14-day delay usually does not suddenly cause major damage.
The problem is more likely to progress over months rather than days:
Crowding → abnormal eruption path → displacement/rotation → increasing difficulty creating space → potentially more complicated orthodontic treatment.
So 14 days is generally not an emergency purely because of the tooth positioning shown here.
If the patient develops infection
That is completely different.
If there is:
- facial swelling
- rapidly increasing gum swelling
- fever
- pus
- severe spontaneous pain
- difficulty swallowing
- difficulty breathing
- swelling spreading toward the eye/neck
then do not wait 14 days.
A dental infection can escalate much faster than an orthodontic problem.
4. Expected treatment/healing timeline
The exact treatment depends on what the dentist finds clinically.
Scenario A — retained baby tooth / creating eruption space
- Examination and X-rays: same day
- Extraction if necessary: usually one appointment
- Gum healing: approximately 7–14 days
- Underlying bone remodeling: several weeks to months
- Permanent tooth eruption/position correction: months
Scenario B — orthodontic space creation
- Diagnosis/planning: 1–3 appointments
- Space creation: generally months
- Tooth movement: commonly several months or longer
- Retention afterward: required to stabilize the result
Scenario C — impacted tooth requiring surgical exposure
- Surgical procedure: generally one appointment
- Initial soft-tissue healing: roughly 1–2 weeks
- Orthodontic traction/eruption: potentially several months
- Final position: often significantly longer than 14 days
So if someone says "it will heal in 14 days," that generally means the soft tissue may heal substantially, not that the tooth-position problem itself has been completely corrected.
5. What could "scale up" if ignored?
For the radiographic appearance you provided, I would rank the potential progression approximately:
Current concern
→ anterior crowding/eruption abnormality
→ tooth displacement
→ worsening lack of space
→ rotation/ectopic eruption
→ possible root interference
→ more complicated orthodontic treatment
The highest concern is not the 14-day period itself. It is allowing an eruption/crowding problem to remain untreated for many months during active dental development.
If infection develops, however, the risk category changes immediately.
6. What I would do next
I would not extract anything based on this X-ray alone.
A reasonable clinical sequence is:
Step 1: Dentist/orthodontist examination
Step 2: Determine patient's age and eruption stage
Step 3: Obtain panoramic/periapical imaging if necessary
Step 4: Identify every permanent and primary tooth accurately
Step 5: Determine whether there is retained primary tooth, ectopic eruption, impaction, supernumerary tooth, or simply normal developmental overlap
Step 6: Assess available arch space
Step 7: Decide whether observation, extraction, space maintenance, or orthodontic treatment is appropriate
Step 8: Establish follow-up interval
My overall radiographic impression
Orthodontic/eruption concern: MODERATE → potentially HIGH depending on age and clinical findings.
Obvious acute infection on this image: LOW.
Immediate life-threatening finding visible on this image: NONE apparent.
But the absence of an obvious lesion on this one radiograph does not rule out disease elsewhere.
Severe Tartar Buildup on Lower Front Teeth: Dental Treatment, Gum Disease Risks, and Tooth Crowding
Clinical Case Analysis: Why Heavy Tartar Around the Lower Front Teeth Requires Professional Treatment
Severe tartar buildup around the lower front teeth is a common dental finding that can indicate inadequate plaque removal and an increased risk of gum inflammation. When thick, hardened deposits accumulate along the gumline and between crowded teeth, cleaning becomes more difficult, allowing bacterial plaque to persist around the teeth and gums.
From a clinical perspective, the priority is not simply to remove the visible yellow or brown deposits. The dentist must also assess the condition of the gums, the supporting bone, the alignment of the teeth, and whether any permanent teeth are impacted or erupting abnormally.
Important clinical distinction: Severe tartar does not automatically mean advanced periodontitis. The severity of gum disease must be established through a periodontal examination, including gum-pocket measurements and assessment of supporting bone.
1. Why Does Tartar Accumulate Behind the Lower Front Teeth?
The inner surfaces of the lower front teeth are common locations for calculus accumulation. Saliva from the nearby salivary gland openings can contribute minerals that help dental plaque harden into calculus.
Several factors can contribute to heavy deposits:
-
Inadequate brushing along the gumline and behind the lower incisors.
-
Failure to clean between the teeth regularly.
-
Crowded or overlapping teeth that are difficult to reach with a toothbrush.
-
Existing gum inflammation and pockets that retain plaque.
-
Individual differences in saliva composition and calculus formation.
Once plaque hardens into calculus, ordinary brushing and flossing cannot remove the deposits completely. Professional dental instruments are required to remove them safely.
2. What Happens When Severe Tartar Is Left Untreated?
Heavy calculus creates an irregular surface where plaque can accumulate. The bacteria in plaque can trigger inflammation in the surrounding gum tissue.
The possible progression is as follows:
Stage 1: Plaque and calculus accumulation
Yellow, white, or brown deposits form along the gumline and between the teeth. The gums may appear red or swollen.
Stage 2: Gingivitis
The gums may bleed during brushing or flossing. Bad breath and tenderness may develop. Gingivitis does not necessarily involve permanent bone loss and is often reversible with professional cleaning and effective daily oral hygiene.
Stage 3: Periodontitis
In some patients, persistent inflammation progresses to destruction of the periodontal attachment and supporting bone. The dentist may detect deeper periodontal pockets, gum recession, or bone loss on dental X-rays.
Stage 4: Tooth mobility or tooth loss
Advanced periodontal disease can weaken the supporting structures of the teeth. Teeth may become loose, shift position, or eventually require extraction if they cannot be maintained.
Not every patient progresses through these stages. Early diagnosis and appropriate treatment can reduce the risk of further damage.
3. How Does Tooth Crowding Affect Tartar Buildup?
Dental crowding occurs when the available space in the dental arch is insufficient for the teeth to align normally. Overlapping teeth create narrow spaces that are difficult to clean effectively.
In a patient with crowded lower incisors, the dentist should examine whether plaque and calculus accumulate between overlapping tooth surfaces and whether the gums show signs of inflammation.
However, crowding and tartar buildup are separate clinical problems. Removing calculus can improve gum health, but it does not straighten the teeth or create additional space in the dental arch.
If crowding contributes to persistent cleaning difficulties, orthodontic assessment may be appropriate after active gum disease has been evaluated and controlled.
4. What Does a Dental X-Ray Reveal About Severe Tartar and Crowding?
A dental X-ray can help the dentist evaluate structures that cannot be assessed adequately by visual examination alone.
Depending on the type and quality of the image, the dentist may assess:
-
The position and development of permanent teeth.
-
Whether a tooth is impacted, displaced, or following an abnormal eruption path.
-
The amount and pattern of supporting bone around the teeth.
-
The relationship between crowded teeth and adjacent roots.
-
Other abnormalities, including certain dental lesions or areas of bone destruction.
A dental X-ray has important limitations. It does not reliably show the full extent of soft plaque, all visible tartar deposits, gum bleeding, or periodontal pocket depth. A clinical examination remains necessary.
The dentist should also avoid assuming that every unusual bone-like structure between primary and permanent teeth represents a disease. The finding must be interpreted according to the patient's age, dental development, clinical examination, and appropriate imaging.
5. Professional Treatment for Severe Tartar on Lower Teeth
Treatment depends on the amount of calculus, the condition of the gums, and whether periodontal damage is present.
Step 1: Comprehensive dental and periodontal examination
The dentist examines the teeth, gums, bite, and areas of heavy calculus accumulation. Periodontal probing may be used to measure the spaces between the teeth and gums. Dental X-rays may be indicated when the dentist needs to evaluate supporting bone or investigate abnormal tooth eruption.
Step 2: Professional scaling
A dentist or dental hygienist uses appropriate professional instruments, which may include ultrasonic scalers and hand instruments, to remove hardened deposits above the gumline and in accessible areas below it.
This procedure removes calculus that cannot be removed with home brushing alone.
Step 3: Scaling and root planing when indicated
If the examination confirms periodontitis with affected periodontal pockets, the dentist may recommend scaling and root planing. This deep-cleaning procedure removes plaque and calculus from below the gumline and cleans affected root surfaces.
Not every patient with heavy visible tartar needs root planing. A routine professional cleaning may be sufficient when there is no evidence of periodontal attachment loss requiring deeper treatment.
Step 4: Reassessment and further periodontal care
After treatment, the dentist reassesses gum inflammation, pocket depths, bleeding, and the patient's ability to maintain oral hygiene.
Persistent deep pockets or advanced periodontal damage may require specialist periodontal treatment. In selected cases, periodontal surgery may be considered.
Step 5: Addressing crowding or abnormal eruption
Once gum health has been assessed and stabilized, the dentist can determine whether the patient needs orthodontic treatment, further imaging, or management of an impacted or displaced tooth.
Orthodontic treatment should be planned with attention to periodontal health because moving teeth in the presence of uncontrolled gum disease can complicate treatment.
6. Can Severe Tartar Be Removed at Home?
No. Hardened calculus cannot be safely removed completely with ordinary brushing, flossing, salt, baking soda, or over-the-counter mouthwash.
Patients should not scrape their teeth with needles, knives, metal tools, or unsterilized instruments. These methods can injure the gums, damage tooth surfaces, and cause infection.
Until professional cleaning is available:
-
Brush twice daily with fluoride toothpaste and a soft-bristled toothbrush.
-
Clean between the teeth daily with floss or appropriately sized interdental brushes.
-
Follow the dentist's advice about any recommended mouth rinse.
-
Avoid smoking or tobacco use, which can worsen periodontal health and interfere with healing.
-
Arrange a dental appointment for professional assessment and calculus removal.
7. Does Severe Tartar Mean a Tooth Must Be Extracted?
No. Heavy tartar alone is not an indication for tooth extraction.
The dentist determines whether a tooth can be preserved by examining its mobility, periodontal attachment, supporting bone, root condition, and overall restorability.
Many teeth affected by calculus and gingivitis can be maintained after professional cleaning and improved oral hygiene. Teeth with advanced periodontal destruction may require more complex treatment, and extraction is considered only when the tooth's prognosis and available treatment options justify it.
The treatment objective is to preserve healthy teeth whenever reasonably possible, control periodontal disease, and maintain comfortable chewing function.
8. When Should a Patient Seek Urgent Dental Care?
Arrange a dental examination promptly if the gums bleed repeatedly, remain swollen, produce pus, or are associated with persistent bad breath or loose teeth.
Seek urgent dental care for significant facial or gum swelling, rapidly worsening pain, or fever associated with a suspected dental infection.
Seek emergency medical care immediately if swelling causes difficulty breathing or swallowing, or spreads toward the eye or neck.
Antibiotics do not remove tartar and are not routinely needed for uncomplicated calculus buildup or gingivitis. If a separate bacterial infection is present, the dentist determines whether medication and additional treatment are necessary.
Frequently Asked Questions
1. Why is tartar especially common behind the lower front teeth?
Saliva from nearby salivary gland openings contributes minerals that can harden plaque. This makes the inner surfaces of the lower front teeth common sites for calculus formation, particularly when plaque is not removed regularly.
2. Can severe tartar cause gum recession?
Tartar-associated inflammation can contribute to periodontal disease, which may lead to gum recession and loss of supporting tissue. However, gum recession has other causes, so a dentist must evaluate the individual case.
3. Can severe tartar cause loose teeth?
Tartar itself does not directly make a healthy tooth loose. When plaque-associated inflammation progresses to periodontitis and damages the supporting attachment and bone, tooth mobility may develop.
4. Is ultrasonic scaling safe for crowded lower teeth?
Professional ultrasonic scaling is commonly used to remove calculus. The dentist or hygienist selects appropriate instruments and technique according to the patient's dental condition, restorations, sensitivity, and periodontal needs.
5. Will scaling remove the crowding?
No. Scaling removes plaque and calculus. Orthodontic treatment is used to correct tooth alignment when appropriate.
6. How often should patients have their teeth professionally cleaned?
The interval depends on the patient's calculus formation, gum health, periodontal history, and ability to control plaque at home. Some patients need more frequent periodontal maintenance, while others may require less frequent visits. The dentist should recommend an individualized schedule.
7. Can I whiten my teeth before removing severe tartar?
Professional assessment and removal of heavy calculus should come first. Tartar can obscure the natural tooth surface and interfere with evaluating tooth color. Whitening does not remove calculus or treat gum disease.
8. Is severe tartar always a sign of poor oral hygiene?
Not necessarily. Inadequate plaque removal is an important factor, but individual differences in saliva, tooth position, access for cleaning, and other risk factors also influence calculus formation. A dentist can help identify the relevant factors without assuming a single cause.
Finding a Cebu dentist through your directory
Your CebuDentalImplants.com Map Dental Clinic specifically provides a location-based directory for finding dental clinics.
Open the CebuDentalImplants.com Dental Clinic Map
The directory currently includes clinics in Cebu City, Mactan/Lapu-Lapu and Talisay, among other locations. For example, it lists D&G Dental Clinic, Ruflo Dental Clinic, Healthy Smile Dental Center–SM Seaside, ESL Dental Clinic Tabunok, and Almario Dental at Ayala Central Bloc.
Dental X-Ray Expert Analysis: Severe Tooth Crowding, Eruption Problems & What Can Happen Without Treatment
A dental X-ray can provide important information that cannot be seen during a routine visual examination. In cases of severe tooth crowding, an X-ray may help a dentist evaluate the position of unerupted or impacted teeth, the available space in the dental arch, tooth roots, surrounding bone, and other factors that may affect treatment planning.
However, an X-ray image should not be interpreted by itself. A dentist or orthodontist must combine the radiographic findings with an intraoral examination, dental history, photographs, bite assessment, and, when appropriate, additional imaging.
What an X-Ray May Show in Severe Crowding
When teeth are significantly crowded, several findings may require careful assessment:
-
Teeth positioned outside their normal eruption path
-
Unerupted or partially erupted permanent teeth
-
Teeth overlapping one another on the image
-
Reduced space available for an erupting tooth
-
Rotated or displaced teeth
-
Possible impaction
-
Abnormal angulation of tooth roots
-
Areas where roots appear unusually close together
-
Bone and supporting structures around the teeth
-
Existing cavities or root-related abnormalities that may influence treatment
A panoramic X-ray is often useful for obtaining an overall view of the developing and erupted teeth. In selected cases, an orthodontist or oral and maxillofacial specialist may recommend additional imaging, such as a CBCT scan, when three-dimensional information is necessary.
Expert X-Ray Voice: What the Dentist Is Looking For
Dentist:
"When I review an X-ray of a severely crowded dentition, I am not simply looking at how crooked the teeth appear. I am evaluating the position of each tooth, its eruption pathway, the amount of available space, the relationship between the roots, and whether any tooth may be blocked from erupting normally."
Orthodontic perspective:
"Severe crowding can occur when the available space in the dental arch is insufficient for the size and position of the teeth. The treatment plan depends on the patient's age, growth and development, facial characteristics, bite, tooth position, periodontal health, and the amount and location of crowding."
Important:
An X-ray alone cannot determine the exact treatment plan. The dentist must correlate the image with the clinical examination.
What Happens When a Tooth Cannot Erupt Normally?
A permanent tooth normally follows an eruption pathway toward the oral cavity. When there is insufficient space or another physical obstruction, eruption can become delayed, displaced, or completely blocked.
A tooth that remains trapped in the bone or under another tooth may become impacted.
The consequences vary from person to person. Possible complications can include:
-
Persistent retention of a baby tooth
-
Delayed eruption of a permanent tooth
-
Displacement of neighboring teeth
-
Increased difficulty maintaining oral hygiene
-
Food accumulation around partially erupted teeth
-
Tooth decay
-
Gum inflammation
-
Damage to adjacent teeth in some cases
-
Cystic changes around an impacted tooth in uncommon cases
Not every impacted or unerupted tooth causes symptoms or requires immediate removal. The appropriate management depends on the tooth involved, its position, the patient's age, symptoms, surrounding structures, and the expected risks and benefits of treatment.
Why Severe Crowding Should Be Evaluated
Crowding is not simply a cosmetic concern.
When teeth overlap substantially, cleaning between them can become more difficult. Plaque accumulation may increase the risk of tooth decay and gum inflammation.
Severe crowding can also make orthodontic treatment more complex because the clinician must determine how to create or redistribute space while maintaining healthy tooth positions and periodontal support.
Early assessment can be particularly important in children and adolescents because some eruption problems can be identified before they become more difficult to manage.
Possible Treatment Approaches
Treatment is individualized. Depending on the case, an orthodontist may consider:
1. Orthodontic Alignment
Braces or clear aligners may be used to gradually reposition teeth and improve alignment.
2. Space Creation
In selected cases, orthodontic treatment can create or redistribute space to allow a displaced tooth to move toward a more favorable position.
3. Tooth Extraction
Extraction may sometimes be recommended when there is severe crowding or when a particular tooth cannot be accommodated safely within the planned dental arch.
Extractions should not be assumed to be necessary simply because an X-ray shows crowding. The decision requires a complete orthodontic assessment.
4. Surgical Exposure and Orthodontic Traction
If a permanent tooth is impacted but considered suitable for preservation, an oral surgeon and orthodontist may work together.
A surgical procedure can expose the tooth, after which orthodontic forces may gradually guide it toward the dental arch.
5. Observation
Some unerupted or impacted teeth may be monitored when immediate treatment is not indicated.
Regular clinical and radiographic follow-up can help determine whether the tooth is changing position or creating a developing problem.
What If Severe Crowding Is Left Untreated?
The outcome depends on the underlying cause and severity.
Untreated crowding may remain relatively stable in some individuals, while in others it can contribute to worsening alignment, difficulty cleaning, localized gum problems, or complications associated with an unerupted or impacted tooth.
Importantly, untreated does not automatically mean that serious damage will occur. A dentist must assess the individual risk rather than predict a complication from an X-ray alone.
If an impacted tooth is suspected, delaying assessment can sometimes make future management more complicated, particularly when neighboring teeth or surrounding structures are affected.
When Should You See an Orthodontist?
Consider an orthodontic evaluation when there is:
-
Severe visible crowding
-
A permanent tooth that has not erupted as expected
-
A baby tooth that remains unusually long
-
Significant tooth rotation or displacement
-
A suspected impacted tooth
-
Difficulty cleaning between crowded teeth
-
A bite that appears substantially abnormal
-
An X-ray showing an unusual eruption path
Children and teenagers may benefit from evaluation during dental development because the timing of intervention can be important in certain eruption problems.
Important Medical Guidance
A dental X-ray should be interpreted by a qualified dental professional who has access to the patient's clinical examination and complete dental history.
Online images or educational descriptions cannot establish a diagnosis.
If an X-ray shows a severely displaced, unerupted, or impacted tooth, the patient may need evaluation by an orthodontist, general dentist, or oral and maxillofacial surgeon, depending on the specific finding.
Seek prompt dental evaluation if there is significant swelling, facial swelling, fever, severe pain, difficulty swallowing, difficulty breathing, or rapidly worsening symptoms.
Frequently Asked Questions
Can severe tooth crowding prevent a permanent tooth from erupting?
Yes. Severe crowding can reduce the available space and may contribute to abnormal eruption or impaction. However, the exact cause must be determined from the clinical and radiographic examination.
Can an X-ray tell if a tooth is impacted?
An X-ray can often show whether a tooth is unerupted and its approximate position and angulation. Additional imaging may sometimes be necessary to understand the three-dimensional relationship between the tooth and surrounding structures.
Does every impacted tooth need to be removed?
No. Some impacted teeth can be monitored, while others may require orthodontic treatment, surgical exposure, extraction, or another approach. The decision depends on the individual circumstances.
Can crowded teeth cause gum disease?
Crowding can make effective brushing and flossing more difficult, which may increase plaque retention and contribute to gingivitis or periodontal problems. Crowding itself is not the same thing as gum disease.
Can braces fix severe crowding?
In many cases, orthodontic treatment can significantly improve crowding. The treatment approach depends on the amount of crowding, tooth position, bite, bone and gum health, facial characteristics, and other factors.
Are teeth always extracted for severe crowding?
No. Extraction is only one possible treatment strategy. An orthodontist evaluates whether sufficient space can be created or redistributed without compromising function, stability, and periodontal health.
What happens if an impacted tooth is ignored?
Some impacted teeth remain problem-free, while others can cause complications such as infection, damage to neighboring teeth, or cystic changes. Monitoring may be appropriate in selected cases, but the risk should be assessed by a dentist.
Is a panoramic X-ray enough for orthodontic diagnosis?
A panoramic X-ray provides valuable information, but orthodontic diagnosis normally requires more than one image. Clinical examination, photographs, bite analysis, dental models or scans, and other radiographs may be used when appropriate.
Is CBCT necessary for every crowded-tooth case?
No. CBCT provides three-dimensional information but should not automatically be used for every orthodontic patient. It may be considered when conventional examination and radiographs do not provide sufficient information for diagnosis or treatment planning.
Can a dentist diagnose tooth crowding from an X-ray alone?
No. The X-ray is one part of the diagnostic process. The dentist or orthodontist needs to combine radiographic findings with the patient's clinical examination and dental history.
Does severe crowding always get worse with age?
Not necessarily. Dental alignment can change over time, but the degree and cause of change vary considerably between individuals. A professional assessment is more reliable than assuming that crowding will inevitably worsen.
What specialist should evaluate a severely crowded or impacted tooth?
An orthodontist is commonly involved when tooth position, eruption, and crowding are the main concerns. An oral and maxillofacial surgeon may become involved when surgical management is required. A general dentist can coordinate the initial evaluation and referral.
A severe-crowding X-ray should be viewed as a diagnostic clue rather than a diagnosis by itself. The most important questions are whether every permanent tooth has a safe eruption pathway, whether adequate space exists, whether any tooth is impacted or displaced, and whether the surrounding teeth, bone, and gums remain healthy.
Early professional assessment can help identify eruption problems and allow the dental team to choose between monitoring, orthodontic space management, surgical exposure, extraction, or other treatment when appropriate.
Clinical Conclusion
Severe calculus on the lower front teeth warrants professional assessment, especially when it occurs alongside crowded teeth, bleeding gums, bad breath, gum recession, or tooth mobility.
The appropriate approach is to remove calculus professionally, determine whether gingivitis or periodontitis is present, evaluate supporting bone when indicated, and address crowding or eruption abnormalities separately.
The key clinical principle is to treat the condition that is actually present—not to diagnose advanced gum disease or recommend extraction based solely on the appearance of tartar or a dental X-ray.
Medical information note: This article is intended for patient education and does not replace an individualized examination, diagnosis, or treatment plan from a licensed dental professional.
Related Clinical Cases
Patients with lower front gum inflammation may also experience tartar buildup, periodontal disease, gum abscesses, or tooth decay. Explore these related clinical case studies.