Healthy Teeth, Happy Life.

Dental Case Analysis: Unusual Bone-Like Structure Between Primary and Permanent Teeth in a Child
Image:
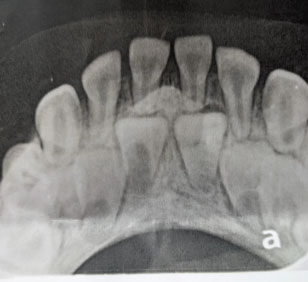
Severity:
Teeth Problems:
Unusual Bone-Like Structure Between Baby Teeth and Permanent Teeth in a Child — What Parents Should Know
Clinical Perspective: Is It Extra Bone, an Extra Tooth, or Normal Jaw Anatomy?
When an unusual hard structure is discovered between a child's primary teeth and developing permanent teeth, the first priority is to determine whether it represents normal anatomy, a developmental dental abnormality, or a lesion that requires treatment.
During mixed dentition—the period when baby teeth and permanent teeth are present together—the jaw contains several developing structures. Their overlapping appearance on a dental X-ray can sometimes make normal anatomy look abnormal.
A bone-like finding should therefore be assessed systematically rather than diagnosed from its appearance alone.
1. What Could Cause an Unusual Bone-Like Finding?
Several conditions may be considered during a pediatric dental examination.
Odontoma: An odontoma is a benign developmental abnormality composed of dental tissues. A compound odontoma may resemble several miniature teeth, while a complex odontoma usually appears as an irregular, dense mass. Some odontomas interfere with the eruption of permanent teeth.
Supernumerary tooth: This is an additional tooth beyond the normal number. When located between the upper central incisors, it is commonly called a mesiodens. Depending on its position and orientation, it may delay eruption, displace neighboring teeth, or cause spacing problems.
Normal anatomical overlap: Dental radiographs are two-dimensional representations of three-dimensional structures. The chin, jawbone, developing teeth, and surrounding anatomy may overlap in ways that create an unusual radiographic appearance. A clinician must determine whether the finding represents genuine pathology or an imaging-related appearance.
Other developmental or bone abnormalities: A localized area of dense bone or another odontogenic lesion may occasionally resemble an abnormal growth. Its precise location, borders, relationship to developing teeth, and clinical findings help guide the differential diagnosis.
These are possibilities to investigate, not confirmed diagnoses for the child described in the source case.
2. Signs That Deserve a Closer Dental Examination
Parents should arrange an assessment with a pediatric dentist if they notice:
-
One permanent front tooth erupting much later than the corresponding tooth on the opposite side.
-
A baby tooth remaining in place when its permanent successor appears delayed.
-
A firm lump in the gum or jaw that persists or increases in size.
-
Teeth becoming displaced, crowded, or unusually spaced.
-
Repeated swelling or discomfort around the affected area.
Some developmental dental abnormalities cause no pain. The absence of pain does not establish that a finding is harmless, particularly when a permanent tooth's eruption may be obstructed.
3. How Dentists Determine What the Structure Is
A responsible diagnostic process generally includes the following steps.
Step 1: Clinical examination
The dentist examines the gums, neighboring teeth, tooth mobility, jaw contour, and eruption pattern. The child's dental history and previous radiographs may also be reviewed.
Step 2: Review of the original X-ray
The dentist evaluates the image quality, angulation, and anatomical landmarks. If overlapping structures make interpretation difficult, a different view may be more informative than immediately ordering advanced imaging.
Step 3: Additional imaging when justified
Depending on the clinical findings, a periapical, occlusal, or panoramic radiograph may help identify the structure and its relationship to developing teeth.
Cone-beam computed tomography (CBCT) provides three-dimensional information, but it should not be automatic for every unusual finding. It is considered when the additional information is expected to affect diagnosis, surgical planning, or another important treatment decision. Children should receive only imaging that is clinically justified, using appropriate radiation-minimization measures.
Step 4: Specialist evaluation
A pediatric dentist, oral and maxillofacial surgeon, orthodontist, or oral and maxillofacial radiologist may be involved depending on the suspected condition. If a genuine lesion remains uncertain, further assessment—and occasionally tissue examination—may be necessary.
4. Does Every Bone-Like Structure Need Surgery?
No. Treatment depends on the confirmed diagnosis and whether the finding threatens the child's oral health or normal dental development.
-
Normal anatomical overlap: No treatment is needed for the appearance itself.
-
A small, harmless finding without complications: Clinical monitoring and appropriately timed follow-up imaging may be sufficient.
-
An odontoma or extra tooth obstructing eruption: Surgical removal may be recommended when the expected benefits outweigh the risks.
-
An impacted permanent tooth: After removing an obstruction, the dentist may monitor spontaneous eruption or recommend orthodontic assistance if necessary.
-
An uncertain or concerning lesion: Additional investigation is required before selecting treatment.
The timing of treatment is particularly important in children because the roots of permanent teeth may still be developing. Removing a structure too early or operating without adequate planning can potentially injure neighboring teeth or their developing roots.
5. What Parents Can Do While Waiting for the Appointment
If the child is otherwise well and the finding is stable, follow the treating dentist's advice about the timing of specialist assessment.
Parents should:
-
Keep the original dental X-rays and request copies of any previous images.
-
Attend the recommended specialist appointment.
-
Avoid pressing, puncturing, or attempting to remove the hard structure at home.
-
Maintain gentle brushing and normal oral hygiene around the area.
-
Ask whether the finding is affecting the eruption of a permanent tooth and when reassessment is needed.
Seek urgent dental or medical assessment if the child develops rapidly increasing swelling, significant pain, fever with facial swelling, or difficulty opening the mouth. Difficulty breathing or swallowing, or rapidly spreading swelling involving the face or neck, requires emergency medical care.
6. What Is the Outlook?
The outlook depends on the cause. Normal anatomical overlap requires no treatment. Many odontomas and supernumerary teeth can be managed successfully, although the eruption of an affected permanent tooth may require additional monitoring or orthodontic treatment.
The most important objective is to establish an accurate diagnosis while protecting the developing permanent teeth. Parents should not assume that an unusual radiographic appearance means cancer, but they should not dismiss a persistent lump or an eruption problem without professional assessment.
Clinical takeaway: A bone-like structure between primary and permanent teeth is a finding to investigate, not a diagnosis. Careful examination, appropriate imaging, and individualized treatment planning provide the safest path forward.
Frequently Asked Questions
1. Can a child develop extra bone between baby teeth and permanent teeth?
An unusual hard structure may represent normal anatomy, a supernumerary tooth, an odontoma, or another developmental finding. The term “extra bone” should not be used as a confirmed diagnosis until a dentist has assessed the clinical findings and relevant images.
2. Is an odontoma dangerous?
Odontomas are generally benign developmental abnormalities rather than cancer. However, an odontoma can interfere with tooth eruption or affect neighboring teeth. A dentist determines whether observation or removal is appropriate.
3. Can an extra tooth prevent a permanent tooth from coming in?
Yes. A supernumerary tooth can obstruct the eruption pathway or displace a developing permanent tooth. Dental imaging can help establish its position and guide management.
4. Could the unusual structure simply be part of the child's chinbone?
Yes, that is possible. Two-dimensional dental X-rays can show overlapping anatomical structures, particularly when the image is angled in a way that makes interpretation difficult. A dentist should review the original image and decide whether another view is needed.
5. Does a painless lump mean that it is harmless?
No. Some developmental dental abnormalities are painless. A persistent or enlarging lump should be examined, especially if permanent teeth are delayed or displaced.
6. Does every child with this finding need a CBCT scan?
No. CBCT is not a routine first step for every unusual dental finding. Conventional dental radiographs and clinical examination may provide sufficient information. Three-dimensional imaging is considered when it is expected to change diagnosis or treatment planning.
7. Will the permanent tooth erupt after an obstruction is removed?
It may erupt spontaneously, but this is not guaranteed. The outcome depends on the child's age, the tooth's position and development, available space, and the duration of the obstruction. Follow-up examinations help determine whether orthodontic assistance is needed.
8. Can parents wait several months before seeing a dentist?
That depends on the clinical findings. A stable finding without symptoms may not require emergency treatment, but a suspected eruption obstruction or unexplained lump should be assessed within the timeframe recommended by the dentist. Do not postpone a specialist referral without discussing the risks with the treating clinician.
9. Can an odontoma or extra tooth cause crooked permanent teeth?
Yes. If the structure obstructs eruption or displaces neighboring teeth, it can contribute to misalignment or spacing problems. Early assessment helps the dentist plan appropriate monitoring or intervention.
10. What questions should parents ask a pediatric dentist?
Useful questions include:
-
What are the leading possible explanations for the structure?
-
Could this be normal anatomical overlap?
-
Is a permanent tooth being obstructed or displaced?
-
Which X-rays are necessary, and would CBCT change the treatment plan?
-
Is monitoring sufficient, or is removal recommended?
-
What are the risks of waiting?
-
How will we monitor the eruption of the permanent teeth?
11. Can this condition be diagnosed from an online dental photograph or X-ray?
An online image may help explain possible conditions, but it cannot reliably establish a diagnosis. Image quality, viewing angle, clinical examination, dental development, and sometimes additional imaging are essential to accurate interpretation.
12. When should parents seek urgent care?
Seek prompt assessment for increasing swelling, severe or worsening pain, unexplained tooth mobility, or a rapidly enlarging lump. Fever with facial swelling requires urgent assessment. Difficulty breathing or swallowing is an emergency.
Medical Disclaimer
This article provides general educational information and does not replace an examination by a licensed dental professional. The possible causes discussed above are differential diagnoses, not a confirmed diagnosis for the individual child. Treatment decisions should be based on the child's examination, appropriate diagnostic imaging, dental development, and specialist recommendations.
A Parent's Concern
Few things create more anxiety for parents than hearing a dentist say, "I'm not sure what this is."
When a child undergoes a routine dental examination and an X-ray reveals an unexpected structure inside the jaw, it can immediately raise concerns about tumors, abnormal bone growth, developmental disorders, or future problems with permanent teeth.
In this case, the dentist identified an unusual radiopaque (white) structure located between the developing permanent teeth and the primary teeth. Because the appearance was not typical, a referral to a specialist located approximately 150 miles away was recommended.
Naturally, the family wants to understand what they may be dealing with before making the long trip.
Important Disclaimer
A definitive diagnosis cannot be made from a single X-ray image alone.
A pediatric dentist, oral surgeon, or orthodontist will need to perform:
- Clinical examination
- Additional radiographs
- Possibly a CBCT scan (3D imaging)
- Review of the child's dental history
- Evaluation of tooth eruption patterns
However, we can discuss the most likely possibilities based on the radiographic appearance.
What Does the X-Ray Show?
The radiograph appears to show:
- Mixed dentition stage
- Developing permanent incisors
- Retained primary teeth
- An unusual radiopaque mass between the teeth
- Delayed eruption pathway of some permanent teeth
The structure appears denser than surrounding bone and is located in an area where normal tooth eruption should occur.
This is why the dentist likely recommended specialist evaluation.
Is This Really "Abnormal Bone Growth"?
Not necessarily.
Parents often describe these findings as "extra bone" because that is what they appear to be on X-rays.
However, several different conditions can create a similar appearance:
- Odontoma
- Supernumerary tooth
- Eruption obstruction
- Developmental dental anomaly
- Dense bone island
- Compound odontogenic lesion
Some are extremely common and benign.
Most Likely Possibility: Odontoma
One of the first conditions many specialists would consider is an odontoma.
What Is an Odontoma?
An odontoma is a benign developmental growth made from dental tissues.
It is not cancer.
It is not an infection.
It is not contagious.
It develops from the same tissues that form teeth.
Because of this, odontomas often contain:
- Enamel
- Dentin
- Cementum
- Pulp-like tissue
Essentially, the body creates extra tooth material in an abnormal shape.
Why Odontomas Are Often Found in Children
Odontomas frequently appear:
- During childhood
- During mixed dentition
- During permanent tooth eruption
Many children have no symptoms at all.
The condition is often discovered accidentally during routine dental X-rays.
Common Signs
Parents may notice:
- Permanent teeth not erupting
- Teeth coming in crooked
- Delayed tooth eruption
- Unusual spacing
- Retained baby teeth
The child may have absolutely no pain.
Types of Odontomas
Compound Odontoma
A compound odontoma contains many tiny tooth-like structures.
On X-rays they often resemble miniature teeth clustered together.
These commonly occur in the front of the upper jaw.
Complex Odontoma
A complex odontoma appears as a dense irregular mass.
Instead of tiny tooth shapes, it looks like a solid radiopaque structure.
This type can block normal tooth eruption.
Why Specialists May Suspect an Odontoma
Several features support this possibility:
- Child is in eruption age
- Structure appears radiopaque
- Location is near developing permanent teeth
- Eruption pathway may be obstructed
- Appearance differs from normal bone
This does not confirm the diagnosis, but it places odontoma high on the list of possibilities.
Another Possibility: Supernumerary Tooth
A supernumerary tooth is an extra tooth.
Some children develop more teeth than normal.
Mesiodens
The most common extra tooth is called a mesiodens.
It develops between the upper front teeth.
A mesiodens can:
- Block eruption
- Push teeth sideways
- Cause spacing issues
- Create crowding
Many are discovered during childhood.
How It Appears on X-Ray
A mesiodens often appears as:
- Tooth-shaped structure
- Cone-shaped tooth
- Inverted tooth
- Small malformed tooth
Sometimes it can be mistaken for other developmental anomalies.
Another Possibility: Eruption Obstruction
Permanent teeth must travel through bone before appearing in the mouth.
Anything blocking this pathway can create problems.
Examples include:
- Thick fibrous tissue
- Bone irregularities
- Odontomas
- Extra teeth
- Developmental defects
When eruption is delayed, dentists investigate for underlying causes.
Could It Be Cancer?
This is one of the biggest fears parents have.
Fortunately, based solely on this image, there are no obvious classic signs suggesting a malignant process.
Most childhood jaw cancers are extremely rare.
Features that often raise concern include:
- Rapid enlargement
- Bone destruction
- Severe pain
- Facial swelling
- Loose teeth
- Numbness
Those features are not apparent from this image alone.
However, specialist evaluation remains essential.
Could It Be an Infection?
The appearance does not strongly resemble a typical dental abscess.
Most abscesses appear as darker areas on radiographs due to bone loss.
This lesion appears relatively dense and radiopaque.
That makes infection less likely as the primary explanation.
Could It Be Normal Development?
Occasionally, developing permanent teeth overlap in unusual ways on 2D radiographs.
Because X-rays flatten three-dimensional structures into a two-dimensional image, anatomy can sometimes appear unusual.
A specialist may determine that what appears abnormal is actually overlapping structures.
Additional imaging helps clarify this.
Why a Specialist Referral Is Appropriate
Some parents worry when they hear their dentist say they don't know what something is.
In reality, this is often a sign of good professional judgment.
A dentist who recognizes an unusual finding and refers appropriately is acting responsibly.
Specialists have access to:
- Advanced imaging
- Pediatric dental expertise
- Oral pathology knowledge
- Orthodontic evaluation
- Surgical management if necessary
What Will the Specialist Likely Do?
Step 1: Review Medical History
Questions may include:
- Any genetic conditions?
- Delayed tooth eruption?
- Previous trauma?
- Family history of dental anomalies?
Step 2: Clinical Examination
The specialist will assess:
- Missing teeth
- Tooth mobility
- Swelling
- Gum condition
- Bite relationship
Step 3: Additional Imaging
Additional radiographs may include:
- Panoramic X-ray
- Occlusal radiograph
- CBCT scan
A CBCT scan provides a three-dimensional view.
This often reveals exactly what the structure is.
Step 4: Diagnosis
Once imaging is complete, the specialist can determine whether the finding represents:
- Odontoma
- Supernumerary tooth
- Developmental anomaly
- Dense bone island
- Other odontogenic lesion
Potential Treatment Options
Treatment depends entirely on the diagnosis.
Observation
If the lesion is harmless and not interfering with eruption:
- Periodic monitoring
- Follow-up X-rays
- No immediate treatment
may be recommended.
Surgical Removal
If an odontoma or extra tooth blocks eruption:
Minor oral surgery may be advised.
This is often performed under:
- Local anesthesia
- Sedation
- General anesthesia in younger children
Orthodontic Guidance
After removing the obstruction, orthodontic treatment may help guide permanent teeth into position.
Recovery After Surgical Removal
Most children recover quickly.
Typical recovery includes:
First 24 Hours
- Mild swelling
- Minor discomfort
- Soft diet
Days 2–7
- Healing progresses rapidly
- Swelling decreases
Weeks 2–4
- Soft tissue largely healed
Months Later
- Permanent teeth may begin erupting normally
What Happens If Left Untreated?
If the structure is blocking tooth eruption, delaying treatment could result in:
- Impacted permanent teeth
- Crowding
- Orthodontic complications
- Misalignment
- Delayed eruption
The longer the obstruction remains, the more difficult treatment may become.
Questions Parents Should Ask the Specialist
Before leaving the appointment, consider asking:
- What is the most likely diagnosis?
- Is this condition common?
- Does my child need a CBCT scan?
- Is surgery necessary?
- Will permanent teeth erupt normally?
- Could this affect future orthodontic treatment?
- What happens if we wait?
- How often should follow-up imaging be performed?
Reassurance for Parents
While the X-ray certainly shows something unusual, many conditions that create this appearance are benign and highly treatable.
In pediatric dentistry, the most common explanations are developmental dental anomalies such as:
- Odontomas
- Supernumerary teeth
- Eruption obstructions
These conditions are encountered regularly by pediatric dental specialists and oral surgeons.
The referral does not necessarily mean the condition is dangerous. More often, it means additional expertise and imaging are needed to determine exactly what is preventing normal tooth development.
Final Assessment
Based on the radiograph alone, the finding appears more consistent with a developmental dental anomaly than with infection or malignancy. The leading considerations include a compound odontoma, complex odontoma, or a supernumerary tooth (mesiodens-like structure) causing interference with the eruption of the permanent teeth.
Estimated Likelihood (Educational Opinion Only)
- Odontoma: High possibility
- Supernumerary tooth: Moderate to high possibility
- Eruption-related developmental anomaly: Moderate possibility
- Dense bone island: Lower possibility
- Infection: Lower possibility
- Malignancy: Appears unlikely based on this image alone
A pediatric dental specialist should evaluate the child as soon as practical, but this X-ray does not immediately suggest a dental emergency. Most similar cases are successfully treated with monitoring or minor surgical intervention, allowing the permanent teeth to continue developing normally.
"Our 5-Year-Old Child Has Some Issues Our Dentist Has Never Seen Before"
After reviewing the Reddit discussion, the overwhelming consensus from multiple dentists, including a pediatric dentist, was that the X-ray likely does not show abnormal bone growth at all. Most commenters believed the image quality and angle of the X-ray created the appearance of an unusual structure.
Main Opinion From Most Dentists
The majority of dental professionals stated:
- The X-ray is poorly angled.
- The white area appears to be normal chin bone anatomy overlapping the image.
- There is no obvious evidence of a tumor, cyst, extra bone growth, or serious pathology.
- The appearance is likely an X-ray artifact caused by positioning.
Several comments were very direct:
"Nothing wrong here."
"This is just a terrible x-ray."
"That's just part of the chin."
Pediatric Dentist's Opinion
A verified pediatric dentist joined the discussion and stated that the structure appears to be:
- Normal anatomy
- Part of the chin
- Visible because the X-ray was taken at an incorrect angle
The pediatric dentist agreed with the other professionals that there was likely nothing unusual present.
Why It Looks Strange
According to several dentists:
The X-ray appears to be an occlusal film taken at an excessive angle.
This causes:
- Chin bone superimposition
- Overlapping structures
- Distorted appearance
As a result, normal anatomy can appear as a dense mass between developing permanent teeth.
Minority Opinion: Still Keep the Referral Appointment
Although most dentists believed the image was normal, one experienced commenter recommended still attending the specialist appointment.
Their concern was not the "bone growth" itself.
Instead, they noted:
- Possible differences in the pulp chambers of the permanent central incisors
- Slight irregularities around the developing teeth
- Difficulty making a complete diagnosis from a single low-quality X-ray
They suggested additional evaluation might still be worthwhile.
Another Conservative View
One commenter noticed that the structure appeared to be in the eruption path of the permanent incisors.
Their recommendation:
- Monitor the child
- Take another X-ray in 6–12 months
- Verify that permanent teeth continue erupting normally
They did not believe it was an emergency.
Parent Follow-Up Information
The parent later commented that:
"It does look ok but there is a nodule you can feel just below the gum line."
This caused some additional discussion.
However, even after learning about the palpable bump, most professionals still believed the radiographic appearance represented normal anatomy or projection error rather than disease.
Overall Community Consensus
Most Likely Explanation
- Normal chin bone anatomy
- X-ray overlap
- Imaging artifact
- Poor X-ray angle
Less Likely
- Odontoma
- Supernumerary tooth
- Abnormal bone growth
Very Unlikely Based on Comments
- Cancer
- Aggressive lesion
- Serious jaw pathology
Recommended Action
- Keep the specialist appointment if feasible.
- Obtain better quality imaging.
- Consider a repeat occlusal X-ray or CBCT if the specialist feels it is necessary.
- Monitor eruption of the permanent incisors.
Related Clinical Cases
Patients with lower front gum inflammation may also experience tartar buildup, periodontal disease, gum abscesses, or tooth decay. Explore these related clinical case studies.